

The Centers for Medicare & Medicaid Services (CMS) releases new payment rules for calendar year 2027. These rules affect how psychiatrists, psychiatric hospitals, and behavioral health facilities get paid. Three separate rulemakings apply: the Physician Fee Schedule, the Inpatient Psychiatric Facility Prospective Payment System, and the Hospital Outpatient Prospective Payment System.
One rule is already final. The Inpatient Psychiatric Facility Prospective Payment System (IPF PPS) rule for fiscal year 2027 sets new payment rates for psychiatric hospitals. The other two rules remain proposed. CMS plans to finalize the Physician Fee Schedule and Outpatient Prospective Payment System rules in November 2026.
This article covers the major CMS updates affecting psychiatry billing for 2027. It reviews Inpatient Psychiatric Facility PPS updates for FY2027 and the proposed Physician Fee Schedule changes for CY2027. It also covers telehealth and tele-mental health extensions, plus OPPS changes for PHP and IOP services. The final section addresses what these updates mean for psychiatric practices and revenue cycle management.
IPF PPS FY2027: Finalized Changes for Inpatient Psychiatric Facilities
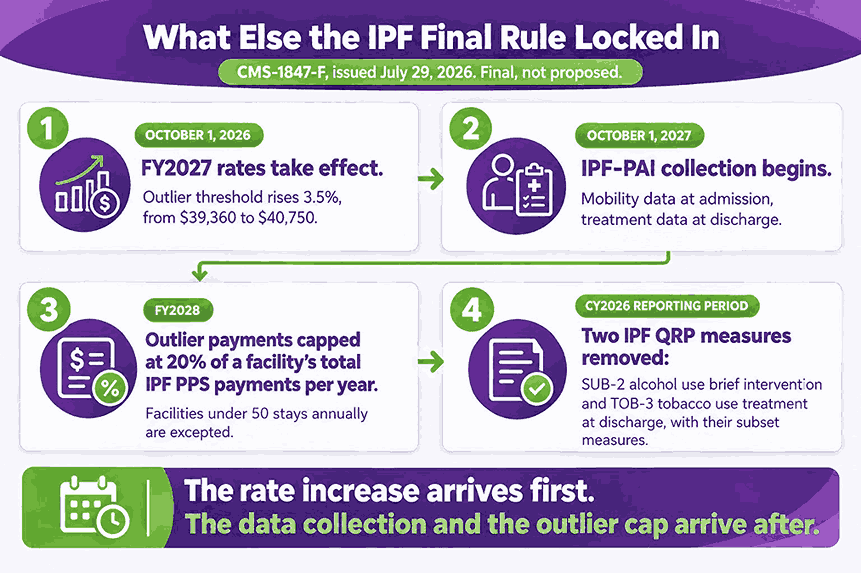
The Inpatient Psychiatric Facility Prospective Payment System rule for fiscal year 2027 covers psychiatric hospitals and psychiatric units inside acute care hospitals. CMS finalized this rule (CMS-1847-F) on July 29, 2026. The rule updates payment rates, quality reporting requirements, and a new patient assessment tool. These changes take effect October 1, 2026.
CMS raised the federal per diem base rate by 2.2 percent. The rate moves from $892.87 to $912.40 for facilities that report quality data. Facilities that fail to report quality measures receive a lower rate of $894.56 per day. Electroconvulsive therapy (ECT) payment also increased by 2.2 percent.
| Payment Item | FY2026 Rate | FY2027 Rate | Change |
|---|---|---|---|
| Federal per diem base rate (compliant reporters) | $892.87 | $912.40 | +2.2% |
| Federal per diem base rate (non-compliant reporters) | n/a | $894.56 | Lower rate |
| Electroconvulsive therapy (ECT) payment per treatment | $673.85 | $688.59 | +2.2% |
New Patient Assessment Requirement
CMS finalized a new standardized data tool called the IPF-Patient Assessment Instrument (IPF-PAI). Facilities must begin using this tool on October 1, 2027. The tool collects mobility data at admission and treatment data at discharge. CMS will use this data for the FY2029 payment determination cycle.
CMS also decided against requiring a Social Security number in the assessment. The Medicare number applies only when Medicare is the primary payer. Facilities can submit IPF-PAI data through two accepted methods, giving smaller psychiatric hospitals flexibility during the rollout period.
Quality Measure Retirements
CMS retired two quality measures starting with the CY2026 reporting period. The removed measures cover alcohol use brief intervention and tobacco use treatment at discharge. Facilities no longer report these measures under the IPF Quality Reporting Program.
The retired measures include:
- SUB-2: Alcohol Use Brief Intervention Provided or Offered
- SUB-2a: Alcohol Use Brief Intervention (subset measure)
- TOB-3: Tobacco Use Treatment Provided or Offered at Discharge
- TOB-3a: Tobacco Use Treatment at Discharge (subset measure)
Inpatient psychiatric facilities benefit from a modest rate increase in FY2027. The tradeoff comes through the IPF-PAI, which adds new data collection work before the FY2029 payment cycle begins.
CY2027 Physician Fee Schedule: Proposed Changes Hitting Outpatient Psychiatry
CMS released the CY2027 Physician Fee Schedule (PFS) proposed rule on July 14, 2026. This rule sets payment policy for outpatient psychiatric services billed under Medicare Part B. The rule identifier is CMS-1848-P. Comments closed September 14, 2026, and CMS plans a final rule in November 2026.
The proposed rule cuts the physician conversion factor (CF). The non-qualifying participant rate drops to $32.8409, a 1.68 percent decrease. The qualifying alternative payment model (APM) rate drops to $33.1693, a 1.19 percent decrease. This cut lowers payment for every psychiatric service billed under the fee schedule.
| Conversion Factor Type | CY2026 Rate | CY2027 Proposed Rate | Change |
|---|---|---|---|
| Non-QP (standard) | $33.4009 | $32.8409 | -1.68% |
| QP (advanced APM participant) | $33.5675 | $33.1693 | -1.19% |
Psychotherapy Code Valuation Increase
CMS proposes the final year of a four-year increase to psychotherapy code values. This increase applies to CPT codes 90832, 90834, and 90837. The adjustment raises work relative value units (RVUs) for timed behavioral health services. CMS began this transition in the CY2024 Physician Fee Schedule rule.
For CY2027, CMS proposes extending the same increase to smoking and tobacco use cessation codes. Screening, Brief Intervention, and Referral to Treatment (SBIRT) codes receive the same treatment. This aligns behavioral health payment increases across a wider set of timed services.
Codes affected by this final-year valuation increase:
- CPT 90832 (30-minute individual psychotherapy)
- CPT 90834 (45-minute individual psychotherapy)
- CPT 90837 (60-minute individual psychotherapy)
- Smoking and tobacco use cessation codes
- SBIRT (Screening, Brief Intervention, and Referral to Treatment) codes
Psychiatric Collaborative Care Model Gets a Valuation Bump
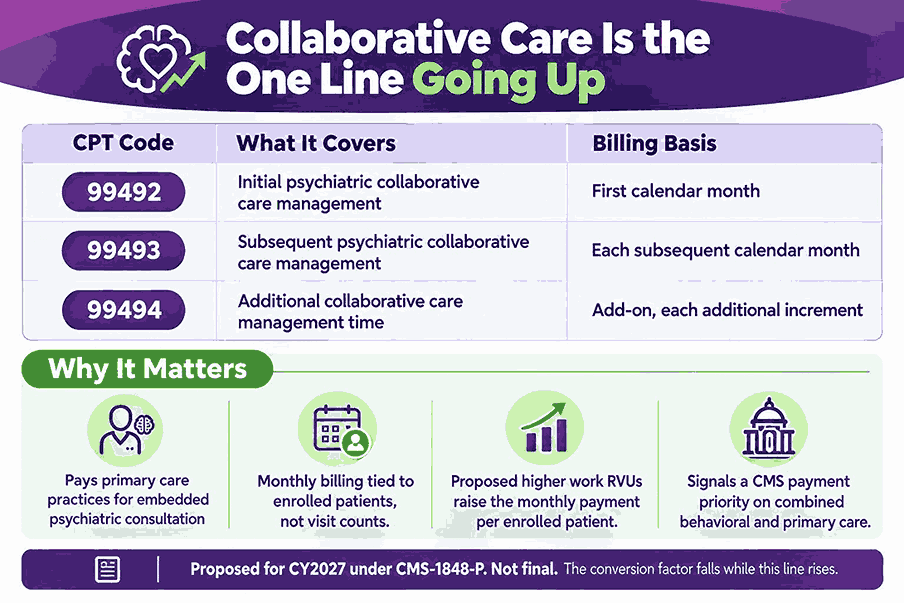
CMS proposes higher work RVUs for the Psychiatric Collaborative Care Model (CoCM). This model uses CPT codes 99492, 99493, and 99494. The Collaborative Care Model connects psychiatric consultants with primary care teams. Higher valuation signals CMS wants more practices adopting this model.
A higher work value increases the monthly payment practices receive per patient. This change rewards psychiatric consultants who support primary care teams through structured, billable collaboration.
Why the Collaborative Care Model matters for psychiatry practices:
- Pays primary care practices for embedded psychiatric consultation
- Uses monthly billing codes tied to patient outcomes, not visit counts
- Higher RVUs mean higher monthly reimbursement per enrolled patient
- Signals a CMS payment priority on combined behavioral and primary care
The proposed rule also touches Medicare Shared Savings Program (MSSP) policy, adjusting shared savings rates for accountable care organizations (ACOs). This matters for health systems and ACOs running psychiatric consultation programs inside larger value-based contracts.
Remote Monitoring Rule Changes Affect Behavioral Health Vendors
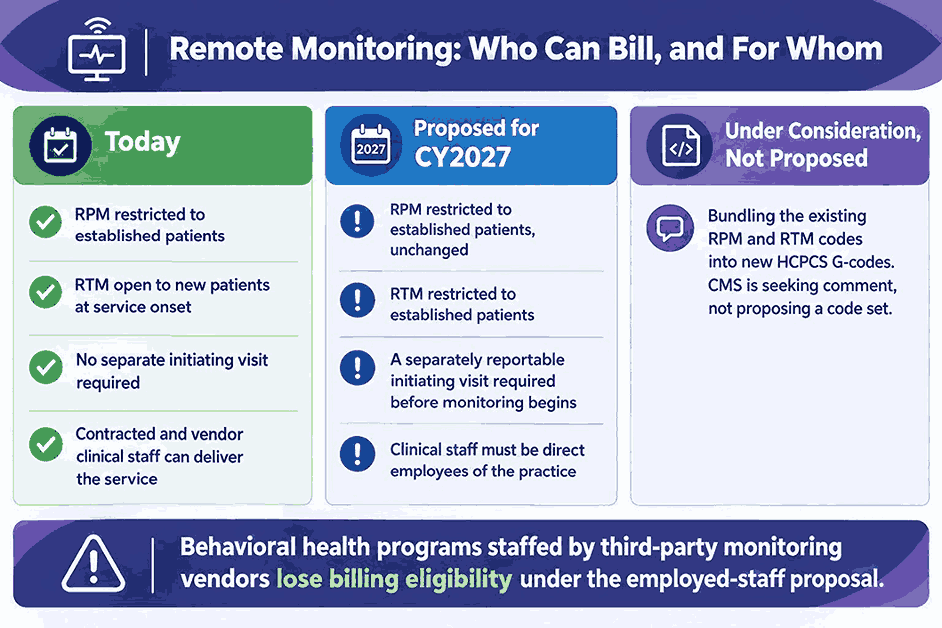
CMS proposes new restrictions on remote physiologic monitoring (RPM) and remote therapy monitoring (RTM) codes. These codes cover devices tracking patient symptoms outside the office. CMS proposes that only established patients qualify for these services. An initiating visit must occur before monitoring begins.
CMS also proposes that only employed clinical staff can deliver these services. Contracted staff would no longer qualify for payment under this rule. This change affects behavioral health practices that outsource remote monitoring work to third-party vendors.
Key proposed changes to RPM and RTM billing:
- Established patients only, no new patients qualify
- A mandatory initiating visit must occur before monitoring starts
- Clinical staff must be direct employees, not contractors
- CMS is also weighing whether to bundle RPM and RTM codes into new G-codes
Other Payment Adjustments to Note
CMS proposes changes to how same-day evaluation and management (E/M) visits get paid alongside procedures. The most expensive service gets paid at 100 percent. Additional services on the same day get paid at 50 percent. This change affects psychiatric consultations billed alongside procedures with global periods.
Telehealth and Tele-Mental Health: What’s Extended, What’s Not
Telehealth remains central to psychiatric care delivery. The Consolidated Appropriations Act of 2026 (CAA 2026) extends key Medicare telehealth flexibilities through December 31, 2027. These flexibilities cover geographic restrictions, originating sites, and eligible practitioners. Psychiatric practices relying on telehealth avoid a coverage cliff in 2027.
Audio-only telehealth coverage also continues through December 31, 2027. The in-person visit requirement for tele-mental health services stays delayed through January 1, 2028. This delay matters for psychiatrists treating patients who cannot travel for an initial in-person visit.
| Telehealth Flexibility | Extended Through |
|---|---|
| Geographic and originating site waivers | December 31, 2027 |
| Audio-only telehealth coverage | December 31, 2027 |
| In-person requirement delay for tele-mental health | January 1, 2028 |
New Telehealth Modifiers Proposed
CMS proposes two new telehealth platform modifiers, BB and BC. These modifiers identify the technology platform used during a telehealth visit. CMS also proposes raising the originating site facility fee for HCPCS code Q3014 to $32.65.
What This Means for Tele-Psychiatry Practices
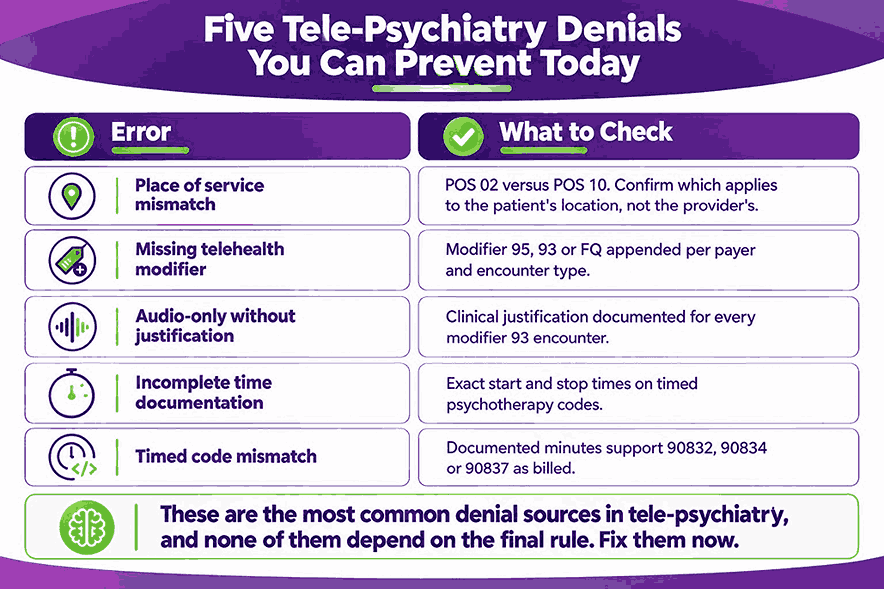
Practices billing psychiatric telehealth visits should confirm current place of service (POS) codes. Common errors include misusing POS 02 instead of POS 10. Missing telehealth modifiers 95, 93, and FQ also trigger claim denials. Documentation of exact session start and stop times matters for timed psychotherapy codes. For full coding and modifier logic beyond telehealth, see our psychiatry billing guide.
Common tele-psychiatry billing errors to check now:
- Place of service code mismatch (POS 02 versus POS 10)
- Missing telehealth modifiers (95, 93, FQ)
- Incomplete start and stop time documentation on timed codes
- Missing clinical justification for audio-only encounters (modifier 93)
CY2027 OPPS Rule: Facility-Based Psychiatric Care (PHP and IOP)
CMS released the CY2027 Hospital Outpatient Prospective Payment System (OPPS) proposed rule on July 2, 2026. The rule identifier is CMS-1850-P. This rule sets payment rates for Partial Hospitalization Programs (PHP) and Intensive Outpatient Programs (IOP). These programs serve patients who need more support than weekly therapy but less than inpatient care.
CMS proposes keeping the current rate structure for PHP and IOP payments. CMS updates the rates using CY2025 claims data. Community Mental Health Centers (CMHCs) continue receiving 40 percent of the hospital-based PHP rate for the same services.
| Setting | Program | Payment Basis | CMHC Rate Adjustment |
|---|---|---|---|
| Hospital outpatient department | Partial Hospitalization Program | Per diem APC | Full hospital rate |
| Hospital outpatient department | Intensive Outpatient Program | Per diem APC | Full hospital rate |
| Community Mental Health Center | Partial Hospitalization Program | Per diem APC | 40% of hospital rate |
| Community Mental Health Center | Intensive Outpatient Program | Per diem APC | 40% of hospital rate |
340B Drug Payment Cuts and Facility Economics
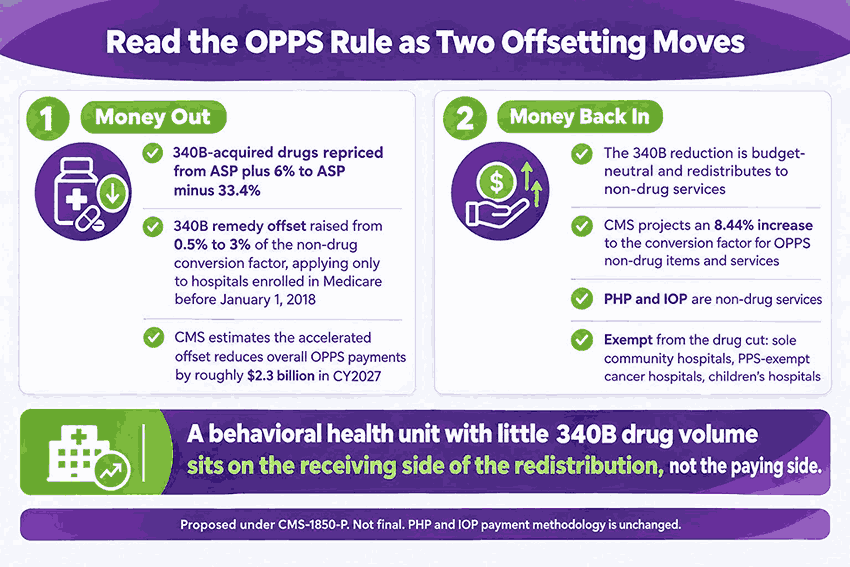
CMS proposes increasing the 340B remedy recoupment adjustment from 0.5 percent to 3 percent. CMS also proposes cutting 340B drug payment to average sales price minus 33.4 percent. These cuts do not target psychiatric services directly. They reduce overall hospital outpatient revenue at facilities running behavioral health units.
Overall OPPS Payment Update
CMS proposes a 2.4 percent increase to overall OPPS rates. This increase applies broadly across outpatient services. Facilities should weigh this general increase against targeted cuts like the 340B payment reduction and the 340B remedy recoupment change described above.
What This Means for Psychiatric Practices and RCM Strategy
These CMS updates create both pressure and opportunity for psychiatric practices. The conversion factor cut lowers payment per service across the Physician Fee Schedule. Practices need stronger coding accuracy and denial management to protect margin. Revenue cycle management (RCM) becomes more important under lower per-unit payment.
Practices without in-house billing depth should evaluate specialized psychiatry billing services now, before the conversion factor cut compounds with CoCM and telehealth complexity.
The Psychiatric Collaborative Care Model increase creates a real growth opportunity. Practices combining psychiatric consultation with primary care can capture higher monthly payment per patient. Billing infrastructure built around CoCM codes stands to gain the most from this change.
Strategic implications for psychiatric practices and RCM teams:
- A lower conversion factor means every claim needs clean coding to avoid revenue loss
- CoCM billing capability becomes a growth lever for combined care models
- IPF-PAI adds new documentation work for inpatient psychiatric facilities
- RPM and RTM restrictions require in-house staffing, not contracted vendors
- Telehealth billing errors remain the most common denial source in tele-psychiatry
Documentation Burden From New Assessment Tools
The IPF-Patient Assessment Instrument adds new data collection work for inpatient psychiatric facilities. Facilities must collect mobility data at admission and treatment data at discharge. This requirement starts October 1, 2027. Facilities without automated workflows face added administrative cost during this transition.
Where Growth and RCM Teams Should Focus
Growth and revenue teams should prioritize denial management for behavioral health telehealth claims first. Second, teams should build billing workflows for Collaborative Care Model codes. Third, teams should audit remote monitoring vendor contracts against the new staffing rule.
Priority actions for 2027 readiness:
- Audit current telehealth billing workflows for POS and modifier accuracy
- Build or expand Collaborative Care Model billing capability
- Review remote monitoring vendor contracts against the employee-only staffing rule
- Prepare inpatient facility workflows for IPF-PAI data collection
- Model conversion factor impact on 2027 revenue projections before budgeting
Key Dates and What to Watch Before Final Rules Publish
The rulemaking timeline for CY2027 psychiatric billing changes spans several months. CMS already finalized the Inpatient Psychiatric Facility rule. The Physician Fee Schedule and Outpatient Prospective Payment System rules remain in proposed form. Both rules typically become final in late October or November.
Comment periods for both proposed rules closed in September 2026. CMS reviews public comments before publishing final rules. Final rule provisions can differ from proposed provisions. Psychiatric practices should track final rule language before adjusting 2027 budgets or billing workflows.
| Rule | Status | Key Date |
|---|---|---|
| IPF PPS FY2027 (CMS-1847-F) | Final | Issued July 29, 2026 |
| Physician Fee Schedule CY2027 (CMS-1848-P) | Proposed | Issued July 14, 2026; comments closed September 14, 2026 |
| OPPS CY2027 (CMS-1850-P) | Proposed | Issued July 2, 2026; comments closed August 31, 2026 |
What Could Still Change
Final rules often adjust proposed conversion factor numbers based on public comment. The Collaborative Care Model valuation increase could shift before finalization. Telehealth modifier proposals could also change. Practices should confirm final numbers once CMS publishes the finalized rules in November 2026.
Final Word
CMS payment changes for 2027 touch every part of psychiatric care delivery. Inpatient facilities gain modest rate increases alongside new assessment requirements. Outpatient practices face a conversion factor cut alongside targeted behavioral health investment. Telehealth access stays stable through 2027, giving tele-psychiatry practices room to plan ahead.
Practices that update billing workflows now avoid denial spikes when final rules take effect. Revenue cycle teams should track CMS updates closely between now and January 2027.

Frequently Asked Questions
What Is The New IPF PPS Per Diem Rate For FY2027?
CMS raised the federal per diem base rate to $912.40 for facilities that report quality data. The rate for non-compliant reporters is $894.56 per day. Both rates take effect October 1, 2026.
How Much Does The CY2027 Physician Fee Schedule Conversion Factor Drop?
The non-QP conversion factor drops 1.68 percent, to $32.8409. The QP rate for advanced APM participants drops 1.19 percent, to $33.1693. CMS plans to finalize this rule in November 2026.
Are Telehealth Flexibilities Extended For Tele-Psychiatry In 2027?
Yes. The Consolidated Appropriations Act of 2026 extends geographic waivers, originating site rules, and audio-only coverage through December 31, 2027. The in-person visit requirement for tele-mental health stays delayed through January 1, 2028.
What Is Changing For The Psychiatric Collaborative Care Model In 2027?
CMS proposes higher work RVUs for CoCM codes 99492, 99493, and 99494. This raises monthly payment for practices that combine psychiatric consultation with primary care. The change signals a CMS payment priority on integrated behavioral health.
What Is The IPF-Patient Assessment Instrument, And When Does It Start?
The IPF-PAI is a new standardized data tool for inpatient psychiatric facilities. It collects mobility data at admission and treatment data at discharge. Facilities must begin using it October 1, 2027, ahead of the FY2029 payment cycle.
Do Community Mental Health Centers Get The Same PHP And IOP Rates As Hospitals?
No. CMHCs continue receiving 40 percent of the hospital-based per diem rate for both Partial Hospitalization and Intensive Outpatient Programs. Hospital outpatient departments receive the full rate for the same services.
What Is Changing For Remote Monitoring (RPM And RTM) Billing?
CMS proposes restricting RPM and RTM codes to established patients only, following a required initiating visit. Only employed clinical staff would qualify to deliver these services. Contracted vendor staff would no longer qualify for payment.
When Will CMS Finalize The CY2027 Physician Fee Schedule And OPPS Rules?
Comment periods for both proposed rules closed by mid-September 2026. CMS typically finalizes fee schedule rules in late October or November. Final numbers can differ from the proposed rates described above.






