

One digit in a BPH diagnosis code can decide whether a urology claim pays or stalls. Benign prostatic hyperplasia is among the most common reasons men see a urologist after age 50. Yet many claims still go out with N40.1 when the note supports N40.0, or the reverse. Payers notice the mismatch, and the denial reaches your desk weeks later.
This blog post explains each BPH ICD-10 code, the symptom codes that pair with it, and the CPT procedures that follow. You will also see documentation rules, common denial triggers, and practical fixes that work.

What BPH Means for Urology Billing?
Benign prostatic hyperplasia means the prostate gland grows larger without being cancerous. The enlarged gland presses on the urethra and irritates the bladder wall. Patients then report a weak stream, urgency, frequent urination, and waking at night to urinate. Urologists group these complaints under lower urinary tract symptoms, often shortened to LUTS.
BPH becomes more common with every decade after age 40. Autopsy data show histologic BPH in roughly 90 percent of men by their eighties. That volume means BPH claims fill a large share of any urology schedule. Small coding mistakes repeat across hundreds of visits, so the revenue impact grows quickly.
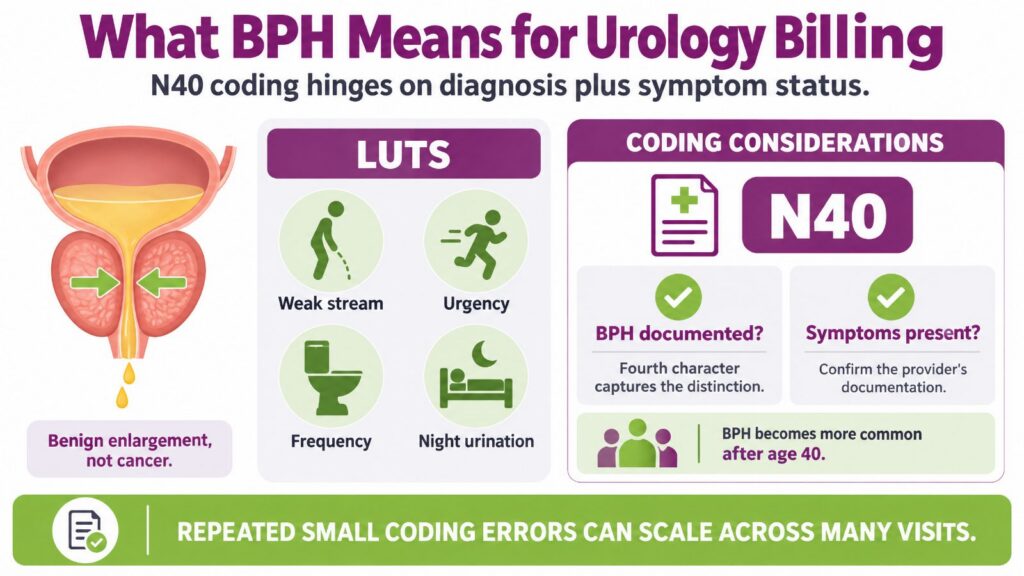
Your diagnosis code must answer two questions: does the patient have BPH, and are symptoms present? The ICD-10 category N40 captures both answers through its fourth character, which is easy to miss. Many urology groups hand this work to a medical billing company that tracks code updates for them.
BPH ICD-10 Codes at a Glance
Category N40 contains four billable codes, and each one describes gland type and symptom status.
| Code | Description | Use When |
|---|---|---|
| N40.0 | Benign prostatic hyperplasia without lower urinary tract symptoms | The provider documents an enlarged prostate and no urinary complaints |
| N40.1 | Benign prostatic hyperplasia with lower urinary tract symptoms | The provider documents an enlarged prostate and at least one urinary symptom |
| N40.2 | Nodular prostate without lower urinary tract symptoms | The provider documents a nodular prostate and no urinary complaints |
| N40.3 | Nodular prostate with lower urinary tract symptoms | The provider documents a nodular prostate and urinary symptoms |
Most BPH visits land on N40.1, because patients usually come in for symptoms.
N40.0 and N40.2: Without Symptoms
Use these codes when the provider documents an enlarged or nodular prostate and the patient reports no urinary problems. A common example is an incidental finding on a digital rectal exam during a routine visit. Another is an enlarged gland seen on imaging ordered for a different reason.
Medical necessity is harder to prove here, since no symptoms justify treatment. Expect closer payer review when a procedure claim carries N40.0 as the only diagnosis.
N40.1 and N40.3: With Lower Urinary Tract Symptoms
Use these codes when the note documents BPH plus at least one urinary symptom. The tabular list instructs coders to add codes for the specific symptoms. This step matters because payers read symptom codes as proof of medical necessity. A claim with N40.1 alone is valid, but it carries less support than one with symptom codes.
Additional Codes for Lower Urinary Tract Symptoms
Pair N40.1 or N40.3 with the symptoms the provider documented in the note. Never add a symptom code only because it seems likely for this diagnosis.
| Symptom | ICD-10 Code |
|---|---|
| Incomplete bladder emptying | R39.14 |
| Nocturia | R35.1 |
| Straining on urination | R39.16 |
| Urinary frequency | R35.0 |
| Urinary hesitancy | R39.11 |
| Urinary urgency | R39.15 |
| Weak urinary stream | R39.12 |
| Other urinary retention | R33.8 |
| Urge incontinence | N39.41 |
| Other obstructive uropathy | N13.8 |
The annual code update takes effect each October 1, so verify codes before billing. A urology ICD-10 code guide also helps coders check related diagnoses beyond BPH.
Here is a simple example. A 68-year-old patient reports a weak stream and nocturia three times nightly. The correct claim lists N40.1 first, then R39.12 and R35.1 as supporting diagnoses. Sequencing matters because N40.1 describes the condition the provider evaluated and treated.
Acute retention needs separate attention. If the patient presents with retention, the provider must document it in clear words. Catheter placement and the retention code then support urgent treatment.
How to Choose the Correct BPH Code
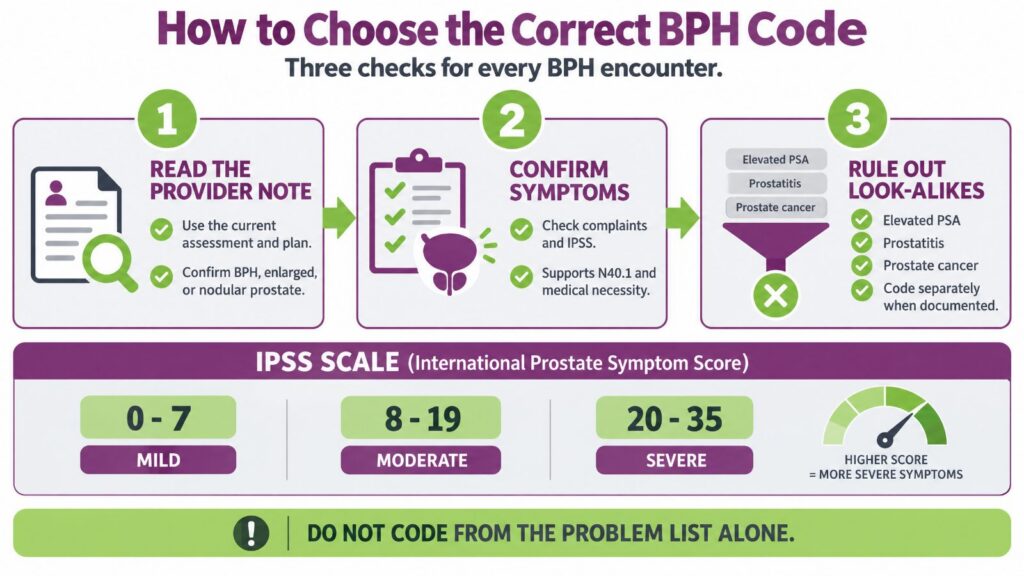
A reliable process prevents most errors. Follow these three checks on every BPH encounter.
Read the Provider Note First
Coders should never pick a code from the problem list alone, since lists go stale. Look for the assessment and plan from the current encounter, and match each diagnosis to it. Confirm that the provider wrote enlarged prostate, BPH, or nodular prostate in clear words.
Confirm Whether Symptoms Exist
Search the note for patient complaints and the symptom score. The International Prostate Symptom Score, or IPSS, rates urinary symptoms from 0 to 35.
| IPSS Range | Severity |
|---|---|
| 0 to 7 | Mild |
| 8 to 19 | Moderate |
| 20 to 35 | Severe |
A documented IPSS score supports N40.1 and strengthens medical necessity for later treatment.
Rule Out Look-Alike Conditions
Elevated PSA, prostatitis, and prostate cancer can all appear in the same note. Each has its own code, and none of them should be folded into N40. If the provider documents BPH and a separate finding, code both only when the note supports it.
BPH Compared With Related Prostate Conditions
Coders often confuse BPH with other prostate diagnoses. This table shows how the codes differ.
| Condition | ICD-10 Code | Key Feature | Coding Point |
|---|---|---|---|
| BPH with LUTS | N40.1 | Enlarged gland with urinary symptoms | Add the symptom codes |
| BPH without LUTS | N40.0 | Enlarged gland, no symptoms | Procedure claims may face medical necessity review |
| Nodular prostate | N40.2 or N40.3 | Nodules found on exam | Use only when the provider documents nodularity |
| Prostatitis | N41.x | Inflammation, often with pain or infection | Choose the specific N41 subcode |
| Elevated PSA | R97.20 | Lab finding with no confirmed cause | Report when the provider documents it as a separate finding |
| Prostate cancer | C61 | Malignant neoplasm | Never replace with an N40 code |
A patient can have BPH and prostate cancer at the same time. In that case, report both codes only when the provider documents both. Never use an N40 code to describe a cancer that biopsy has confirmed.
CPT Codes Commonly Paired With BPH Diagnoses
The diagnosis code explains why the service happened, while the CPT code shows what was done.
Procedures for BPH
| CPT Code | Procedure |
|---|---|
| 52601 | Transurethral resection of the prostate (TURP), complete |
| 52630 | Transurethral resection of residual or regrowth prostate tissue |
| 52450 | Transurethral incision of the prostate |
| 52648 | Laser vaporization of the prostate |
| 52649 | Laser enucleation of the prostate (HoLEP) |
| 53850 | Transurethral microwave thermotherapy |
| 53852 | Transurethral radiofrequency thermotherapy |
| 53854 | Transurethral water vapor thermal therapy (Rezum) |
| 52441 | Permanent adjustable transprostatic implant, first implant (UroLift) |
| 52442 | Each additional implant, reported with 52441 |
Most of these procedures pair with N40.1 or N40.3 and the documented symptom codes. Coverage for newer procedures varies by payer, so check each policy before scheduling. Payers such as Aetna and UnitedHealthcare publish BPH surgical treatment policies with specific criteria. Typical criteria include prostate volume limits, an IPSS score, and a failed medication trial.
Practices that perform these procedures often rely on urology billing services that already know each payer rule.
Office Services Billed With BPH
| CPT Code | Service |
|---|---|
| 99213 or 99214 | Established patient office visit |
| 51798 | Postvoid residual by bladder ultrasound |
| 51736 | Simple uroflowmetry |
| 51741 | Complex uroflowmetry |
| 81001 or 81003 | Urinalysis |
| 84153 | Total PSA |
| 52000 | Diagnostic cystourethroscopy |
Link each service on the claim to the diagnosis that justifies it. For example, 51798 should point to N40.1 and R39.14 when incomplete emptying is documented.
Do not bill G0103 for a symptomatic patient. That code covers screening for men without symptoms. Use 84153 with the matching diagnosis codes instead.
Modifiers That Affect BPH Claims
Modifiers tell the payer how services relate to each other. These are the ones urology teams use most with BPH.
- Modifier 25: Applies when the provider performs a significant, separately identifiable E/M service on the day of a minor procedure.
- Modifier 57: Marks the visit where the provider decided to perform a major procedure, such as TURP, with a 90-day global period.
- Modifier 58: Reports a staged or related procedure during the global period.
- Modifier 78: Reports an unplanned return to the operating room for a complication.
- Modifier 79: Reports an unrelated procedure during the global period.
- Modifier 59 or XU: Supports a distinct service, but only when the documentation proves it.
Each modifier needs support in the note. A modifier without documentation invites an audit. Modifier rules shift by payer, so medical billing services with urology experience can review claims before submission.
Medical Necessity and Documentation Requirements
Correct codes fail without a note that backs them up. Payers read the chart before they pay for a BPH procedure.
What Payers Expect to See
- Symptom history with duration and severity
- IPSS score at baseline and after treatment
- Prostate volume from ultrasound or MRI
- Post-void residual volume when retention is a concern
- Medication trial with drug names, doses, and dates, such as tamsulosin or finasteride
- PSA result and cancer risk assessment
- Reason conservative therapy failed or is not suitable
Sample Documentation That Supports N40.1
Here is a short note that meets most payer standards:
72-year-old male with BPH and LUTS. IPSS 22. Nocturia four times nightly. Weak stream. Postvoid residual 180 mL. Prostate volume 62 mL. Failed six months of tamsulosin 0.4 mg. Plan: Rezum.
This note supports N40.1, R35.1, and R39.12. It also supports R39.14 if the provider documents incomplete emptying. The prostate volume and failed medication trial support the procedure request.
Prior Authorization Rules
Many commercial payers require prior authorization for Rezum, UroLift, and laser procedures. Medicare coverage depends on the local Medicare Administrative Contractor. Verify the policy for your jurisdiction before you schedule the patient. A missed authorization is one of the most expensive errors in BPH billing, because the full procedure payment is at risk.
Common BPH Coding Errors and How to Fix Them
| Error | Result | Fix |
|---|---|---|
| Using N40.0 when symptoms are documented | Weak medical necessity and procedure denials | Review the note and use N40.1 |
| Leaving out symptom codes | Claim lacks clinical support | Add each documented symptom |
| Coding from the problem list | Audit risk | Code from the current assessment |
| Billing G0103 for a symptomatic patient | Service denied as screening | Bill 84153 with diagnosis codes |
| Missing modifier 25 on a same-day E/M | E/M denied as bundled | Add modifier 25 with separate documentation |
| No prior authorization for Rezum or UroLift | Full denial | Verify authorization before scheduling |
| Using an expired code set | Claim rejection | Update code tables every October |
Handling BPH Denials Quickly
Denials on BPH procedures usually trace back to missing documentation or authorization. Track each denial by payer, CPT code, and reason code, so patterns appear. Dedicated denial management support can appeal quickly and fix the root cause upstream.
Appeal deadlines vary by payer. Medicare allows 120 days from the initial determination to file a first-level appeal. Commercial payers often allow less time, so read each contract.
Best Practices for Urology Practices
Strong BPH billing comes from habits, not heroics. These steps work in practices of any size.
- Train coders and providers on category N40 and the symptom codes every October.
- Build a visit template that captures IPSS, prostate volume, post-void residual, and medication history.
- Verify eligibility and authorization before every procedure date.
- Audit 20 charts per provider each quarter for code accuracy.
- Set claim scrubber edits that flag N40.0 on any procedure claim.
- Review denial reports monthly and share findings with providers.
Practices without in-house coders often rely on RCM services to cover eligibility, coding, and payment posting. That setup lets clinical staff focus on patients instead of payer rules.
Frequently Asked Questions
What Is the ICD-10 Code for BPH?
BPH falls under category N40. Use N40.1 when the patient has lower urinary tract symptoms. Use N40.0 when the provider documents an enlarged prostate with no symptoms.
What Is the Difference Between N40.0 and N40.1?
N40.0 means BPH without lower urinary tract symptoms. N40.1 means BPH with those symptoms. The symptoms must appear in the provider note, not just in the patient history form.
Can I Bill N40.1 Without Symptom Codes?
You can, and the claim is technically valid. However, the tabular list instructs coders to add symptom codes when applicable. Symptom codes also strengthen medical necessity, which protects procedure claims.
Which CPT Code Is Used for TURP?
CPT 52601 reports a complete transurethral resection of the prostate. It includes control of postoperative bleeding. Use 52630 for resection of residual or regrowth tissue.
Does Medicare Cover Rezum and UroLift?
Coverage depends on the local Medicare Administrative Contractor and the patient meeting policy criteria. Check the local coverage determination for your jurisdiction. Document prostate volume, symptom score, and failed medication therapy.
Can BPH and Prostate Cancer Be Coded Together?
Yes, when the provider documents both conditions. Report C61 for the cancer and an N40 code for BPH. Never use N40 as a substitute for a confirmed cancer diagnosis.
When Should I Use Modifier 25 With a BPH Visit?
Use modifier 25 when the provider performs a significant, separately identifiable E/M service on the same day as a minor procedure. For a major procedure with a 90-day global period, use modifier 57 on the decision visit.






