

Z12.11 is the first-listed diagnosis for a screening colonoscopy. Medicare reports G0121 or G0105, commercial plans use CPT with modifier 33, and a screening that turns therapeutic adds modifier PT or 33.
A screening colonoscopy examines the colon of a patient with no symptoms to find polyps or early cancer. ICD-10-CM reports it with Z12.11, which means encounter for screening for malignant neoplasm of colon. The code explains why the procedure happened, not what the physician found.
Procedure coding differs by payer. Medicare uses HCPCS code G0121 for average-risk patients and G0105 for high-risk patients. Commercial plans use CPT codes, such as 45378, with modifier 33. Z12.11 stays on the claim in every case to prove screening intent.
Surgery centers carry extra risk here. A screening can turn therapeutic when the physician removes a polyp, and the claim then needs modifier PT for Medicare or 33 for commercial plans. Patient cost sharing depends on that modifier, so one missing character changes the bill.
The sections below cover the Z12.11 code family, risk and history codes, CPT and HCPCS pairing, and polyp-removal coding. They also cover Medicare rules, ASC claim handling, documentation, common denials, and frequent coding questions from surgery center teams and billing staff.
What Is the ICD-10 Code for Screening Colonoscopy?
The ICD-10 code for screening colonoscopy is Z12.11, encounter for screening for malignant neoplasm of colon. Searches for icd 10 screening colonoscopy and colonoscopy screening icd 10 all lead to this code. It applies to asymptomatic patients, and coders list it first when screening is the reason for the visit.
Z12.12 reports screening for malignant neoplasm of rectum, which applies to rectal screening rather than a colonoscopy. The dx code for screening colonoscopy stays Z12.11 even when the exam is normal. The table below lists the codes that appear on most screening claims and the role each one plays.
| ICD-10 Code | Description | Role on the Claim |
|---|---|---|
| Z12.11 | Encounter for screening for malignant neoplasm of colon | First-listed for a screening colonoscopy |
| Z12.12 | Encounter for screening for malignant neoplasm of rectum | Rectal screening, not colonoscopy |
| Z80.0 | Family history of malignant neoplasm of digestive organs | Risk code that explains high-risk status |
| Z83.71- | Family history of colonic polyps | Risk code for relatives with polyps |
| Z85.0- | Personal history of malignant neoplasm of digestive organs | Risk code after colorectal cancer |
| Z86.0100 to Z86.0109 | Personal history of colon polyps, by polyp type | History code listed after the screening code |
| K63.5 | Polyp of colon | Finding code when a polyp is found |
| D12.- | Benign neoplasm of colon | Finding code after pathology confirms an adenoma |
Family history of colon cancer icd 10 searches usually mean Z80.0, and history of colon polyps icd 10 searches mean the Z86.010 family. Both are secondary codes on a screening claim. The broader ICD-10-CM code set follows the same first-listed and secondary logic for other screening encounters.
When Is a Colonoscopy Screening, Surveillance, or Diagnostic?
A screening colonoscopy is performed on a patient without symptoms to look for polyps or cancer. Surveillance colonoscopy is a subset of screening, done at an interval shorter than the standard ten years. Diagnostic colonoscopy investigates a symptom, a sign, or an abnormal test result.
Finding a polyp during a screening exam does not change the screening intent. A patient with rectal bleeding or anemia is having a diagnostic colonoscopy from the start. The table below answers the screening vs diagnostic colonoscopy coding question by intent.
| Type | Typical Patient | First-Listed Diagnosis | Medicare Code | Commercial Treatment |
|---|---|---|---|---|
| Screening, average risk | No symptoms, no polyp history | Z12.11 | G0121 | CPT with modifier 33 |
| Screening, high risk | Family or personal history of polyps or cancer | NCD 210.3 risk code for Medicare; Z12.11 on many commercial claims | G0105 | CPT with modifier 33 |
| Surveillance | Prior polyps, follow-up interval | Payer-specific | G0105 when high risk | Some plans treat it as diagnostic |
| Diagnostic | Symptom, sign, or abnormal test | The symptom or finding | CPT 45378 without PT | Standard diagnostic benefit |
Payers define these categories differently, and that difference drives most disputes. Diagnostic vs screening colonoscopy insurance coverage changes patient cost sharing, so the category decides what the patient owes. The difference between screening and diagnostic colonoscopy always traces back to the documented reason for the exam.
How Does Surveillance Fit Between Screening and Diagnostic?
Surveillance colonoscopy follows a prior polyp or cancer and uses an interval shorter than ten years. A Medicare contractor example covers a patient with a personal history of adenomatous polyps. When the physician notes surveillance, the visit may qualify as high-risk screening under G0105. Commercial plans vary by policy.
- Medicare: high-risk screening with G0105 when the history meets the NCD 210.3 criteria.
- Commercial: screening, diagnostic, or a separate surveillance benefit, depending on the plan.
- Documentation: prior pathology, polyp type, and the date of the last exam.
How Do You Sequence Z12.11 With Risk and History Codes?
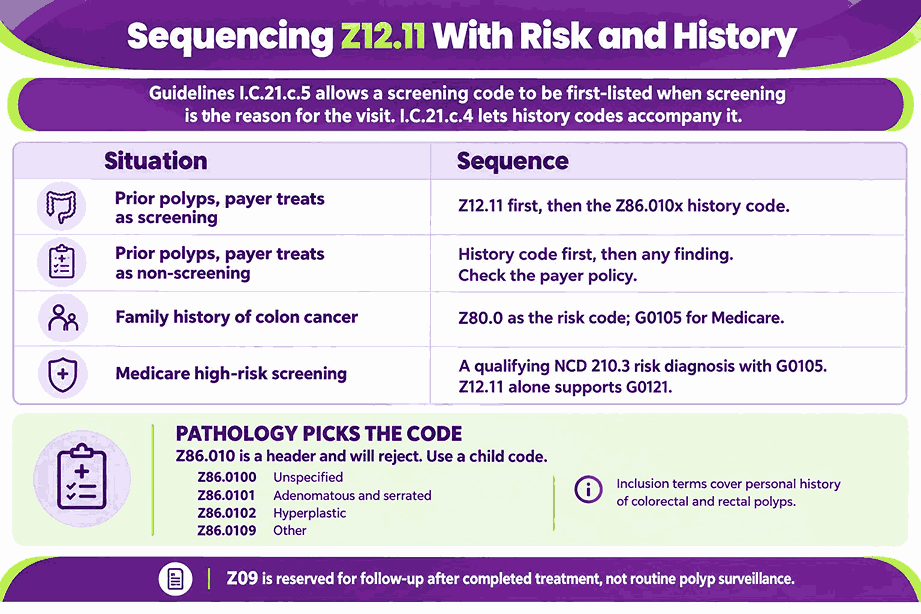
ICD-10-CM Official Guidelines Section I.C.21.c.5 allows a screening code to be first-listed when screening is the reason for the visit. Section I.C.21.c.4 lets family history codes accompany screening codes to explain the need for the test. Personal history codes follow the same additional-diagnosis pattern.
Medicare high-risk claims work differently. A high-risk screening colonoscopy reports G0105 with a qualifying risk diagnosis from National Coverage Determination (NCD) 210.3, such as a personal history of adenomatous polyps. Z12.11 alone supports G0121 for average-risk patients, and a mismatch between code and diagnosis can trigger medical necessity edits.
- Prior polyps, payer treats as screening: Z12.11 first, then the Z86.010x history code.
- Prior polyps, payer treats as non-screening: the history code first, then any finding. Check the payer policy.
- Family history of colon cancer: Z80.0 as the risk code, with G0105 for Medicare.
- Z09 follow-up code: reserved for follow-up after completed treatment. AAPC coding guidance advises against it for routine polyp surveillance.
Surveillance colonoscopy icd 10 and high risk screening colonoscopy icd 10 questions now hinge on the new history codes. Z86.010 is a header, and the histology-based children took effect on October 1, 2024. Z86.0101 reports adenomatous and serrated polyps, Z86.0102 reports hyperplastic polyps, Z86.0109 reports other types, and Z86.0100 reports unspecified. Pathology picks the code.
How Do Family History Codes Change the Claim?
Family history codes explain risk, and they rarely replace Z12.11. Z80.0 reports a family history of malignant neoplasm of digestive organs, which covers colorectal cancer in a parent, sibling, or child. Z83.71- reports a family history of colonic polyps, with child codes by polyp type.
- Close relative with colorectal cancer: Z80.0 as the risk code.
- Close relative with an adenomatous or serrated polyp: Z83.710 as the risk code.
Which Procedure Codes Pair With Z12.11?
Medicare screening claims use HCPCS G0121 for patients not at high risk and G0105 for high-risk patients. Searches for a medicare g code for screening colonoscopy end here. Commercial plans typically accept CPT 45378 with modifier 33 when the exam is a screening.
The screening colonoscopy cpt code question has two answers because payers differ. CPT 45378 describes the diagnostic colonoscopy, while G0121 and G0105 describe the screening service for Medicare. Modifier 33 flags a preventive service on commercial claims. The table below pairs each scenario with its codes.
| Scenario | Medicare | Commercial (Typical) | Diagnosis Order |
|---|---|---|---|
| Average risk, no findings | G0121 | 45378 with 33 | Z12.11 |
| High risk, no findings | G0105 | 45378 with 33 | Risk diagnosis; Z12.11 per payer |
| Biopsy during screening | 45380 with PT | 45380 with 33 | Z12.11, then the finding |
| Snare polypectomy | 45385 with PT | 45385 with 33 | Z12.11, then K63.5 or D12.- |
| Follow-on after positive stool test | G0121 or G0105 with KX | Payer-specific | Z12.11 |
Coders who pick the cpt code for screening colonoscopy first often miss the diagnosis pairing. The ASC CPT codes guide explains how modifiers and NCCI edits shape each procedure line. That detail matters most when a screening adds a biopsy or polypectomy.
How Do You Code a Screening Colonoscopy That Turns Therapeutic?
A screening that turns therapeutic keeps its screening diagnosis. The coder reports the CPT code for the procedure performed, appends modifier PT for Medicare or 33 for commercial plans, and lists Z12.11 first. The polyp or lesion code follows as the finding.
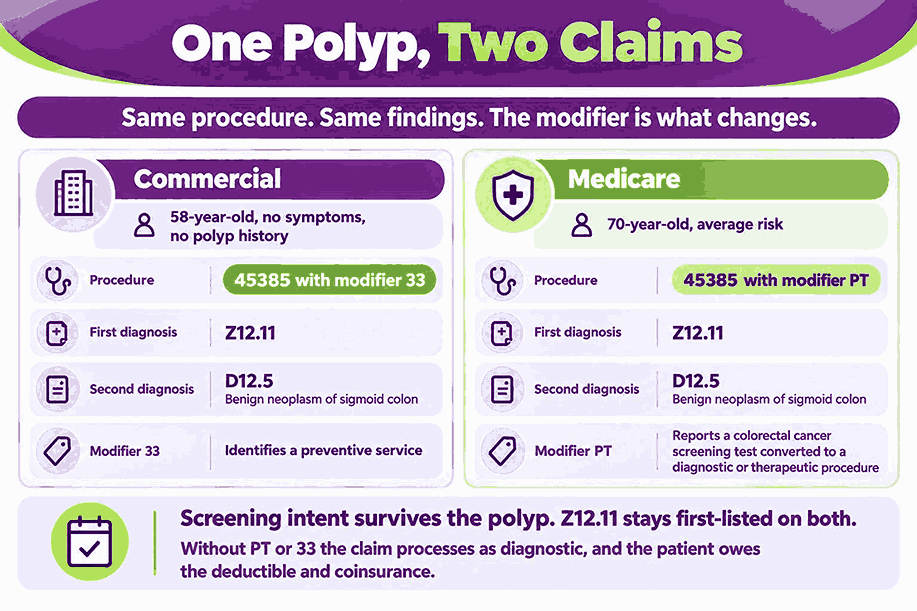
Modifier PT tells Medicare that a colorectal cancer screening test was converted to a diagnostic or other procedure. Modifier 33 does the same job for commercial preventive benefits. Without either one, the claim processes as diagnostic, and the patient may owe the deductible and coinsurance.
| Step | Action | Example |
|---|---|---|
| 1 | Confirm screening intent in the pre-procedure record | Asymptomatic patient, average risk |
| 2 | Code the procedure performed | 45385 for snare polypectomy |
| 3 | Append the modifier | PT for Medicare, 33 for commercial |
| 4 | List Z12.11 first | Z12.11 |
| 5 | Add the finding | K63.5, or D12.- after pathology |
| 6 | Check the payer rule on modifier placement | Which claim lines carry PT or 33 |
What Does a Medicare Patient Owe After a Screening Turns Therapeutic?
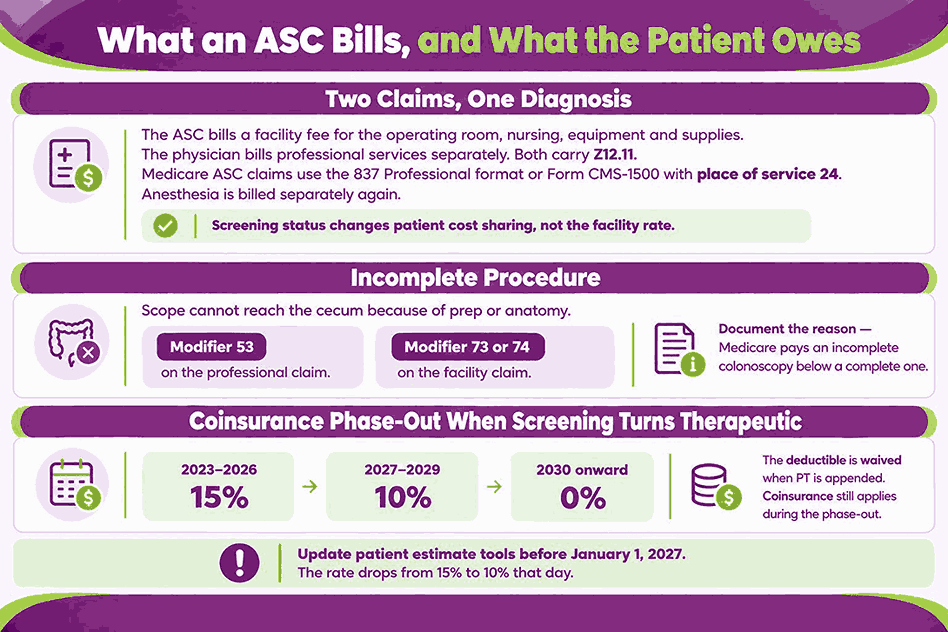
Medicare waives the deductible when modifier PT is appended, but coinsurance applies during a phase-out. The rate is 15% for dates of service in 2023 through 2026, drops to 10% for 2027 through 2029, and ends in 2030. ASCs should update patient estimate tools before January 1, 2027.
| Calendar Year | Coinsurance When Screening Turns Therapeutic |
|---|---|
| 2023 to 2026 | 15% |
| 2027 to 2029 | 10% |
| 2030 and later | 0% |
What Does a Worked Example Look Like?
A 58-year-old patient with commercial insurance has no symptoms and no polyp history. The physician removes one polyp by snare technique, and pathology reports a tubular adenoma in the sigmoid colon. The claim reports a screening that became therapeutic, so modifier 33 applies on a commercial plan.
- Procedure line: 45385 with modifier 33.
- First diagnosis: Z12.11.
- Second diagnosis: D12.5, benign neoplasm of sigmoid colon.
A 70-year-old Medicare patient at average risk follows the same pattern with modifier PT in place of 33. The finding code follows Z12.11 on the claim. The patient owes coinsurance on the therapeutic portion at the phase-out rate for the year of service.
What Are the Medicare Rules for Screening Colonoscopy?
Medicare covers screening colonoscopy for patients age 45 and older under NCD 210.3 and 42 CFR 410.37. The CMS 2023 Physician Fee Schedule final rule lowered the starting age from 50 to 45. Coverage frequency depends on whether the patient is at high risk.
For patients not at high risk, Medicare covers a screening colonoscopy once every 120 months, or 48 months after a flexible sigmoidoscopy. For high-risk patients, the interval is 24 months. A claim inside the interval can deny, so eligibility checks before scheduling protect the facility fee.
- A parent, sibling, or child with colorectal cancer or an adenomatous polyp.
- Family history of familial adenomatous polyposis.
- Family history of hereditary nonpolyposis colorectal cancer.
- Personal history of adenomatous polyps.
- Personal history of colorectal cancer.
Since January 1, 2023, a follow-on colonoscopy after a positive stool-based test counts as screening. Providers append modifier KX to G0105 or G0121 for it, and frequency limits do not apply. If polyps are removed during that exam, the claim uses the CPT code with modifier PT instead.
Which Stool-Based Tests Lead to a Follow-On Colonoscopy?
Medicare covers a multitarget stool DNA test once every three years and a screening FIT or guaiac test once every 12 months. A positive result leads to a follow-on screening colonoscopy with no patient cost sharing. Modifier KX confirms that the clinical requirements of the complete colorectal cancer screening policy are met.
How Do ASCs Bill Screening Colonoscopy?
An ASC bills a facility fee for the operating room, nursing, equipment, and supplies, while the physician bills professional services separately. Medicare ASC claims use the 837 Professional format or Form CMS-1500 with place of service 24. Both claims carry the same screening diagnosis.
Chapter 18 of the Medicare Claims Processing Manual pays a covered screening colonoscopy, including the ASC facility fee, like a diagnostic one. Screening status changes patient cost sharing, not the facility rate. Modifier PT still matters because it controls what the patient owes.
- Anesthesia: the anesthesia provider bills it separately from the facility fee.
- Patient estimates: registration tools need a coinsurance update every January during the phase-out.
- Eligibility: risk category and interval checks happen before the surgery date.
How Do ASCs Report an Incomplete Screening Colonoscopy?
An incomplete colonoscopy happens when the scope cannot reach the cecum because of poor prep or anatomy. The physician reports modifier 53 on the professional claim, and the ASC reports modifier 73 or 74 on the facility claim. Medicare pays an incomplete colonoscopy below a complete one, so documentation of the reason matters.
Surgery centers without dedicated endoscopy coders often send these claims to outside teams. Outside teams also track payer changes that small in-house staff miss. Transcure’s ASC billing services cover screening and diagnostic colonoscopy coding for surgery centers, including modifier checks before submission and denial follow-up after payment.

What Documentation Supports Screening Status?
Screening status rests on intent and the absence of symptoms, and both must appear in the record before the procedure. The pre-procedure note should state the reason for the exam, the patient’s risk category, and the date and findings of any prior colonoscopy. Payers read these details during audits.
The operative report then supports the code choice. It records bowel prep quality, how far the scope advanced, and every polyp removed or biopsied. Missing details force physician queries, and queries delay claims. A short template in the endoscopy record prevents most gaps. The list below shows the items to record.
- Reason for the exam and a statement that the patient has no symptoms.
- Risk category and the basis for it.
- Date, findings, and pathology of any prior colonoscopy.
- Prep quality and the extent of the exam.
- Each polyp removed or biopsied, with site and technique.
| Phrase in the Note | Coding Meaning | Next Step |
|---|---|---|
| “Screening colonoscopy, no symptoms” | Screening | Z12.11 first |
| “Rectal bleeding” | Diagnostic | Code the symptom first, no PT |
| “Anemia workup” | Diagnostic | Code the anemia first |
| “Surveillance, history of adenomatous polyps” | High-risk screening or payer-specific | G0105 for Medicare; check commercial policy |
| “Family history of colon cancer” | High risk | Z80.0 as the risk code |
Gastroenterology practices need the pre-procedure note and the operative report to agree on intent and risk category. Transcure’s gastroenterology billing services compare both documents at the coding stage, before the claim reaches the payer. A mismatch found early costs a short query instead of a denial.
What Are the Most Common Screening Colonoscopy Coding Errors?
Most screening colonoscopy denials trace to sequencing, modifiers, and risk coding, not to the procedure itself. Each error below shifts a screening claim into diagnostic processing or triggers a payer edit. Billing teams can audit for these patterns every month.
A monthly sample audit compares each claim with the pre-procedure note and the operative report. Track the share of claims that carry modifier 33 or PT after a polyp removal. A low rate on a polypectomy-heavy schedule usually signals a workflow gap, not a coding gap. The table below lists the errors.
| Error | Result | Fix |
|---|---|---|
| Z12.11 not first-listed | Claim processes as diagnostic | List Z12.11 first for screening encounters |
| Missing 33 or PT after polyp removal | Patient billed deductible and coinsurance | Append the correct modifier |
| Z86.010 parent code reported | Claim rejection | Report Z86.0100 through Z86.0109 |
| G0121 with a non-screening diagnosis | Medical necessity edit | Pair G0121 with Z12.11 |
| G0105 without a qualifying risk diagnosis | Edit or denial | Report an NCD 210.3 risk code |
| Colonoscopy inside the coverage interval | Denial | Verify the 120-month or 24-month interval |
| Modifier 53 on an ASC facility claim | Wrong modifier | Use 73 or 74 on the facility claim |
| Symptomatic patient coded as screening | Audit risk | Code the symptom first |
| Missing KX on a follow-on colonoscopy | Medicare returns the claim | Add KX to G0105 or G0121 |
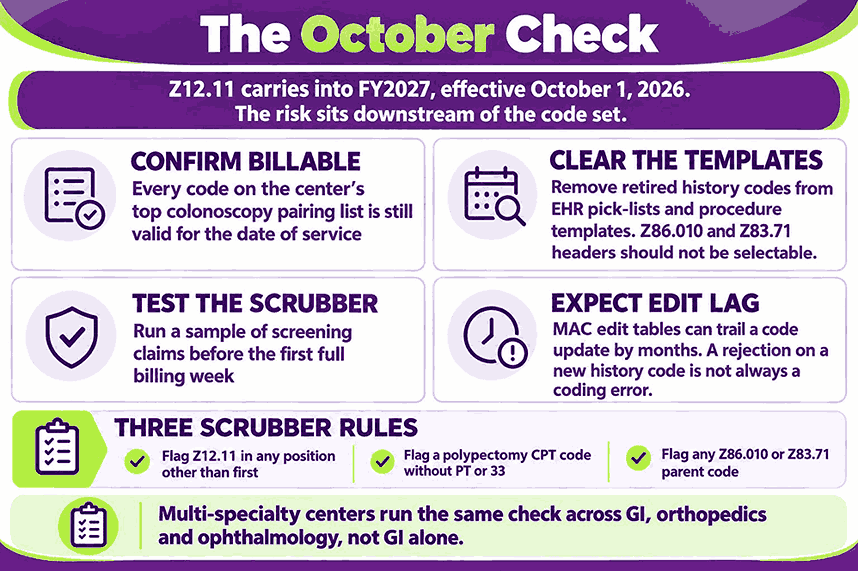
Fixing these errors starts with edits in the scrubber. Three rules catch common problems before submission. One flags Z12.11 in any position other than first. Another flags a polypectomy CPT code without PT or 33, and a third flags any Z86.010 parent code. Denial reports then show which payer rules need a closer look.
Did FY2027 Change Screening Colonoscopy Codes?
Z12.11 remains in the FY2027 ICD-10-CM code set, which took effect on October 1, 2026. Coders should still validate every code against the CMS files for the date of service. The history and family history codes changed in recent update cycles, so older templates may carry retired codes.
MAC edit tables can lag a code update by months. New history codes may reject until the contractor’s edit list catches up, so a rejection does not always signal a coding error. Multi-specialty centers should check the annual update across GI, orthopedics, and ophthalmology, which the ASC ICD-10 codes guide organizes by specialty.
- Confirm that every code on the center’s top colonoscopy pairing list is still billable.
- Remove retired history codes from EHR pick-lists and procedure templates.
- Test a sample of screening claims in the scrubber before the first full billing week.
Frequently Asked Questions
How Do I Code a Screening Colonoscopy?
Code a screening colonoscopy with Z12.11 as the first-listed diagnosis and the procedure code the payer requires. Medicare uses G0121 or G0105, while commercial plans use CPT 45378 with modifier 33. When a polyp is removed, report the CPT code for the removal with modifier PT or 33.
What Are the CMS Guidelines for Screening Colonoscopy?
CMS covers screening colonoscopy for patients age 45 and older under NCD 210.3. Average-risk patients qualify once every 120 months, and high-risk patients qualify every 24 months. Claims use G0121 or G0105, and modifier PT reports a screening that converted to a therapeutic procedure.
What Is the ICD-10 Code for a Pre-Procedure Colonoscopy?
A visit to schedule a screening colonoscopy for an asymptomatic patient uses Z12.11. The code describes the screening purpose, so it fits the planning visit as well as the procedure. Coverage for the visit itself varies by payer, so check the plan before billing an evaluation and management service.
What Is the ICD-10 Code for a Normal Colonoscopy?
A normal screening colonoscopy still reports Z12.11, because the code describes the reason for the encounter and not the result. A normal exam does not need a finding code. Surveillance exams after prior polyps add the matching Z86.010 child code as a secondary diagnosis.
What Is the Difference Between Z12.11 and Z12.12?
Z12.11 reports screening for malignant neoplasm of colon, and Z12.12 reports screening for malignant neoplasm of rectum. A screening colonoscopy uses Z12.11. Z12.12 fits rectal screening encounters, and some Medicare stool-test policies list both codes as covered screening diagnoses. Coders should not substitute one code for the other.
What Is the Difference Between Modifier 33 and Modifier PT?
Modifier 33 identifies a preventive service on commercial claims, while modifier PT identifies a Medicare screening that converted to a diagnostic or therapeutic procedure. Medicare claims use PT, and most commercial payers use 33. Each payer’s policy decides which modifier it accepts.
What Is the Difference Between G0121 and G0105?
G0121 reports a screening colonoscopy on a patient not at high risk, and G0105 reports a screening colonoscopy on a high-risk patient. High-risk status comes from conditions such as a personal history of adenomatous polyps. The interval differs, with 120 months for G0121 and 24 months for G0105.
At What Age Does Medicare Cover a Screening Colonoscopy?
Medicare covers screening colonoscopy for patients age 45 and older. CMS lowered the starting age from 50 to 45 through the 2023 Physician Fee Schedule final rule. High-risk patients may qualify earlier or more often, depending on the documented risk factor.
Does a Screening Colonoscopy Become Diagnostic When a Polyp Is Found?
A screening colonoscopy that finds a polyp keeps its screening intent, but the claim is coded as a therapeutic procedure with modifier PT or 33. Z12.11 stays first-listed. Medicare then applies the coinsurance phase-out to the therapeutic portion, while the screening portion carries no patient cost sharing.
Can One Claim Show Both Screening and Diagnostic Services?
A single claim can show a screening that converted to a diagnostic or therapeutic procedure, which is why modifier PT or 33 exists. The diagnosis list still begins with Z12.11, and the finding codes follow. Patient cost sharing then depends on the modifier and the payer’s policy.
What Is the ICD-10 Code for Surveillance Colonoscopy?
No single code covers every surveillance colonoscopy, because payers treat it differently. Many payers accept Z12.11 first with a Z86.010 child code second. Medicare reports G0105 with a qualifying risk diagnosis, and some commercial plans want the history code first.






