

Allergic rhinitis affects an estimated 10% to 30% of children in the United States, and pediatric practices submit thousands of J30.x claims every allergy season. However, pediatric coding carries risks that adult allergic rhinitis coding does not.
Payers scrutinize pediatric allergy claims more closely because children under 4 rarely qualify for skin testing and immunotherapy requires stricter medical necessity documentation in minors. Furthermore, well-visit coding frequently overlaps with sick-visit allergy evaluation when both services occur on the same date.
Therefore, a pediatric practice billing J30.0 through J30.9 without etiology-specific documentation, correct modifier use, and CPT pairing accuracy exposes itself to denials, audits, and delayed reimbursement.
This pediatrics ICD-10 codes guide on allergic rhinitis breaks down every J30.x subcode, the CPT codes that pair with pediatric allergy visits, the documentation payers require, and the denial patterns specific to pediatric allergic rhinitis claims. Practices that code allergic rhinitis correctly on the first pass avoid the rework cycle that erodes collections and delays A/R.

What Is Allergic Rhinitis & How Does ICD-10 Classify It?
Allergic rhinitis is an inflammatory reaction of the nasal mucosa triggered by an allergen such as pollen, dust mites, animal dander, or food proteins. ICD-10-CM classifies allergic rhinitis under category J30 (Vasomotor and Allergic Rhinitis), located within the J30-J39 block for other diseases of the upper respiratory tract. Category J30 itself is a non-billable header code.
Every claim requires a child code that specifies the rhinitis type and, where documented, the etiology. Pediatric allergic rhinitis frequently co-occurs with three related conditions: allergic conjunctivitis, otitis media with effusion, and asthma (J45). Coders must document each comorbidity separately, since ICD-10 does not bundle allergic rhinitis with these conditions automatically.
Which ICD-10 Codes Classify Allergic Rhinitis Under J30.x?
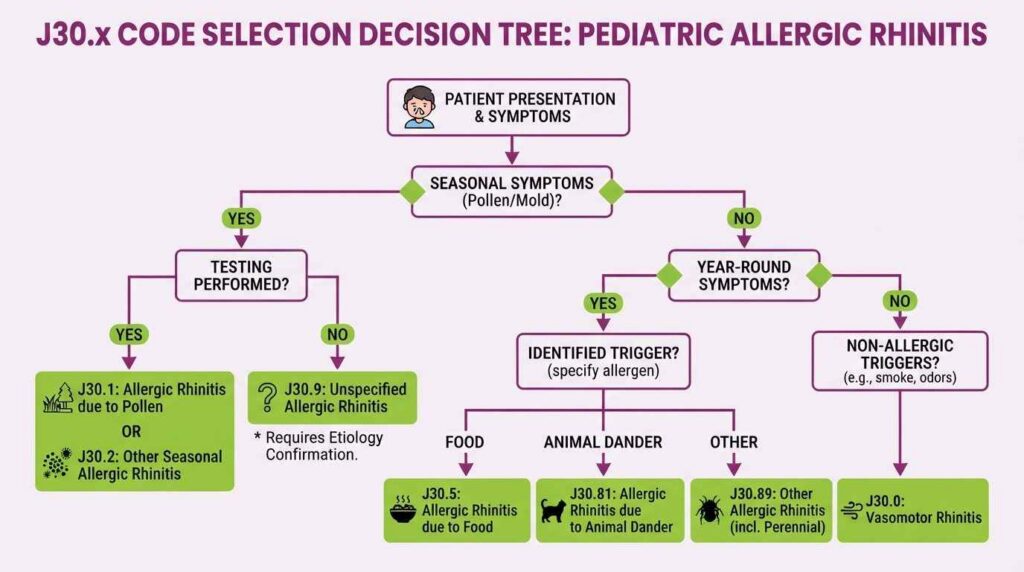
Seven billable subcodes sit under category J30, and each one requires a specific clinical trigger documented in the chart before selection. The table below lists every active J30.x code used in pediatric allergic rhinitis billing.
| ICD-10 Code | Description | Billable | Clinical Trigger for Selection |
|---|---|---|---|
| J30.0 | Vasomotor rhinitis | Yes | Non-allergic triggers: weather change, strong odors, smoke exposure |
| J30.1 | Allergic rhinitis due to pollen | Yes | Documented pollen sensitivity (tree, grass, weed) |
| J30.2 | Other seasonal allergic rhinitis | Yes | Seasonal symptoms from mold spores or dust mites, not pollen |
| J30.5 | Allergic rhinitis due to food | Yes | Confirmed food-triggered nasal symptoms |
| J30.81 | Allergic rhinitis due to animal (cat)(dog) hair and dander | Yes | Documented pet allergen exposure and reaction |
| J30.89 | Other allergic rhinitis (includes perennial allergic rhinitis) | Yes | Year-round symptoms with a non-food, non-animal, non-pollen trigger |
| J30.9 | Allergic rhinitis, unspecified | Yes | Etiology not yet determined or documented |
J30.9 remains billable, but payers increasingly flag repeated use of unspecified codes on established patients as a documentation gap. A pediatric allergist who confirms pollen sensitivity through skin testing must update the claim from J30.9 to J30.1 on the follow-up encounter. Consistent use of J30.9 past the second visit signals incomplete workup to a payer’s medical review team.
How Does Pediatric Allergic Rhinitis Coding Differ From Adult Coding?
Pediatric allergic rhinitis coding differs from adult coding in three specific areas: age-based testing eligibility, comorbidity documentation, and guardian-reported history.
What Age Restrictions Apply to Pediatric Allergy Testing?
Percutaneous allergy testing (CPT 95004) is clinically reliable in children as young as 2, but many payers require additional documentation of symptom duration before approving testing under age 4. Pediatric charts must also capture growth and sleep impact, since allergic rhinitis in children under 12 correlates with mouth breathing, disrupted sleep, and secondary otitis media at higher rates than in adults.
How Does Guardian-Reported History Affect Documentation?
Guardian-reported symptom history carries equal diagnostic weight to child-reported history in ICD-10 documentation, and coders must record which party provided the history in the encounter note. A chart missing this attribution weakens the medical necessity case for testing or immunotherapy on review.
What Documentation Does Medical Necessity Require for Pediatric J30.x Claims?
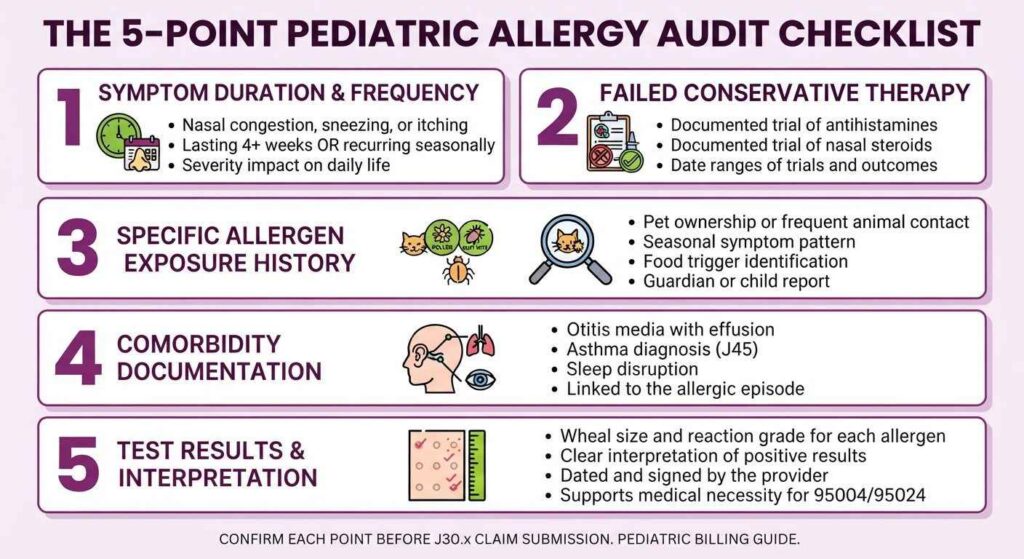
Medical necessity documentation for pediatric allergic rhinitis claims requires five specific elements before a payer approves testing, immunotherapy, or a specialist referral. The table below outlines each requirement and its billing function.
| Documentation Element | What It Must Show | Billing Function |
|---|---|---|
| Symptom duration and frequency | Nasal congestion, sneezing, or itching lasting 4+ weeks or recurring seasonally | Supports medical necessity for testing (95004, 95024) |
| Failed conservative therapy | Documented trial of antihistamines or nasal steroids before testing | Required by most commercial and Medicaid MACs |
| Specific allergen exposure history | Pet ownership, seasonal pattern, or food trigger reported by guardian or child | Supports etiology-specific code selection (J30.1, J30.5, J30.81) |
| Comorbidity documentation | Otitis media, asthma, or sleep disruption linked to the allergic episode | Justifies combined E/M and procedure billing on one date |
| Test results and interpretation | Wheal size, reaction grade, and clinical interpretation for each allergen tested | Required to bill 95004/95024 per unit tested |
Payers deny allergy testing claims most often when the chart shows a diagnosis code but no documented conservative therapy trial. A pediatric practice that bills CPT 95004 without a prior antihistamine trial on record risks a medical necessity denial regardless of how accurate the J30.x code is.
Which CPT Codes Pair With J30.x for Pediatric Allergy Testing and Treatment?
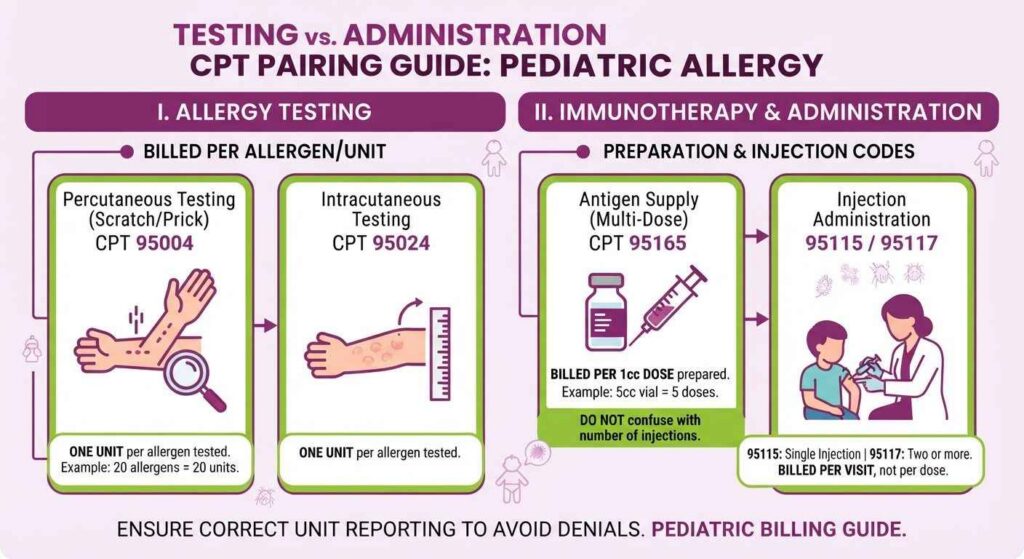
Pediatric allergic rhinitis claims typically pair a J30.x diagnosis code with one of nine CPT codes across testing, immunotherapy, and administration. The table below lists each code and its unit-reporting requirement.
| CPT Code | Service | Unit Basis |
|---|---|---|
| 95004 | Percutaneous (scratch/prick) allergy testing, non-venom | One unit per allergen tested |
| 95017 | Percutaneous testing, venom | One unit per venom tested |
| 95018 | Percutaneous testing, drug | One unit per drug tested |
| 95024 | Intracutaneous (intradermal) testing, non-venom | One unit per allergen tested |
| 95027 | Intracutaneous titration test | One unit per allergen tested |
| 95044 | Patch or application testing | One unit per patch applied |
| 95115 | Immunotherapy, single injection | One unit per visit |
| 95117 | Immunotherapy, two or more injections | One unit per visit |
| 95165 | Antigen supply for immunotherapy, multi-dose vial | One unit per 1cc dose prepared |
CMS requires the exact number of tests performed to appear in the units field for codes 95004 through 95078. A claim listing 20 percutaneous tests must show 20 units against CPT 95004, not a single unit with a note describing 20 tests in free text. Payers process the units field programmatically, and a mismatch between documented tests and billed units triggers an automatic denial before a human reviewer sees the claim.
You can also read our pediatrics CPT codes guide.
How Are E/M Visits Coded Alongside Allergic Rhinitis in Pediatric Patients?
An E/M code billed alongside allergy testing or immunotherapy on the same date requires modifier 25, and the chart must document a separately identifiable evaluation beyond the testing or injection itself.
When Does Modifier 25 Apply to a Same-Day E/M Visit?
Modifier 25 applies whenever a physician performs a distinct, medically necessary evaluation in addition to a same-day procedure. CMS guidance explicitly excludes informed consent for immunotherapy from separate E/M billing, since consent counts as part of the immunotherapy service itself.
How Does Well-Child Visit Coding Interact With Allergy Evaluation?
Pediatric practices commonly encounter overlap during a well-child visit (99381-99385 for new patients, 99391-99395 for established patients) when the physician also addresses new allergic rhinitis symptoms. In that scenario, the well-child visit code and a problem-oriented E/M code (99212-99215) both apply, with modifier 25 appended to the problem-oriented code to signal the distinct component.
What Modifiers Apply to Pediatric Allergic Rhinitis Claims?
Three modifiers appear most frequently on pediatric J30.x claims, and each one carries a distinct documentation trigger.
| Modifier | Use Case | Documentation Trigger |
|---|---|---|
| 25 | Separately identifiable E/M on the same date as testing or immunotherapy | Chart shows a distinct evaluation beyond the procedure note |
| 59 | Distinct procedural service when two allergy procedures occur same-day | Chart distinguishes each procedure by site, session, or allergen group |
| 76 | Repeat procedure by the same provider | Chart documents a second, separate testing session same-day |
Modifier 25 remains the most frequently misapplied modifier on pediatric allergy claims as discussed in pediatrics billing guide. Coders often append it automatically to every E/M code billed alongside testing, without confirming the chart documents a truly separate evaluative component. Payer audits target this pattern specifically in pediatric allergy and ENT practices.
What Are the Most Common Denial Reasons for Pediatric J30.x Claims?
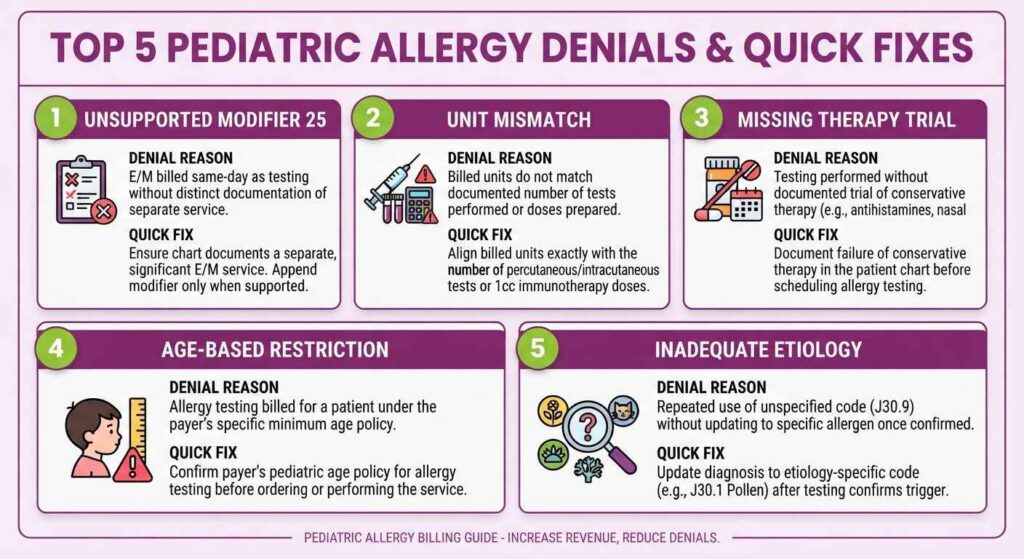
Five denial patterns account for most pediatric allergic rhinitis claim rejections across commercial and Medicaid payers.
| Denial Reason | Root Cause | Fix |
|---|---|---|
| Medical necessity not met | No documented conservative therapy trial before testing | Record antihistamine or nasal steroid trial and its outcome |
| Unspecified code overuse | J30.9 billed repeatedly on an established patient | Update to etiology-specific code once testing confirms the trigger |
| Modifier 25 missing or unsupported | E/M billed same-day as testing without distinct documentation | Document a separate evaluative component or drop the E/M code |
| Unit mismatch | Units billed do not match the number of tests documented | Align the units field exactly with the documented test count |
| Age-based testing denial | Testing billed for a patient under the payer’s age threshold | Confirm payer-specific pediatric age policy before scheduling testing |
Pediatric allergy and ENT practices that audit these five patterns before submission reduce first-pass denials significantly, since all five stem from documentation and unit-reporting gaps rather than incorrect code selection.
How Does Allergen Immunotherapy Billing Work for Pediatric Patients?
Allergen immunotherapy billing for pediatric patients separates into two components: antigen preparation (CPT 95165) and injection administration (95115 or 95117). CPT 95165 defines a dose as a 1cc aliquot from a multi-dose vial, and the units billed must equal the number of 1cc doses prepared, not the number of injections given.
Pediatric immunotherapy claims face closer scrutiny than adult claims because payers require documented parental consent, a defined treatment duration, and periodic reassessment of continued medical necessity, typically every 12 months. A practice that bills 95165 without documenting the total doses prepared per vial preparation session risks a unit-count denial identical to the pattern seen in allergy testing.
What NCCI Edits and Payer Policies Affect Pediatric Allergic Rhinitis Billing?
The National Correct Coding Initiative (NCCI) bundles allergy testing into rapid desensitization procedures (CPT 95180), meaning testing performed as part of a desensitization kit is not separately billable. NCCI also excludes allergen potency testing from separate reimbursement, since potency confirmation counts as an inherent part of immunotherapy preparation.
Additionally, category J30 carries an Excludes1 note against allergic rhinitis with asthma (J45.909), which means coders must never report J30.x and the combined asthma-rhinitis code on the same claim line. Pediatric practices that bill both codes together trigger an automatic system-level rejection, independent of documentation quality.
How Can Pediatric Practices Reduce Denials on Allergic Rhinitis Claims?
Pediatric practices reduce J30.x denial rates by standardizing workflow controls across coding, documentation, and modifier use.
What Workflow Controls Reduce Denial Rates?
Four controls address the majority of pediatric allergic rhinitis denials: etiology-specific code selection at the second visit, mandatory conservative-therapy documentation before testing. Also, automated unit-matching between test counts and billed units, and modifier 25 audits on every same-day E/M and testing claim.
How Does Transcure Support Pediatric Allergy Billing?
Practices running these controls manually across a high-volume allergy season absorb significant coder hours per claim. Transcure applies its AI coding agent, CODIN, to flag etiology-code mismatches and unit discrepancies before submission, which contributes to a 98% first-pass clean claim rate across its pediatric and allergy specialty clients. Transcure’s pediatric billing services cover J30.x-specific claims end-to-end, including credentialing, denial recovery, and A/R follow-up, at a flat 5% of collections regardless of practice size.
Frequently Asked Questions
Is J30 a billable ICD-10 code?
J30 alone is not billable. It functions as a category header, and every claim requires one of its child codes: J30.0, J30.1, J30.2, J30.5, J30.81, J30.89, or J30.9.
Which J30.x code applies when a pediatric patient’s allergy trigger is unknown?
J30.9 (Allergic rhinitis, unspecified) applies when the etiology has not been confirmed through history or testing. Coders should update the code once testing identifies a specific trigger.
Can allergic rhinitis and asthma be billed on the same claim?
No. ICD-10 carries an Excludes1 note between J30.x and combined asthma-rhinitis code J45.909. The two codes cannot appear on the same claim line.
What CPT code covers percutaneous allergy skin testing in children?
CPT 95004 covers percutaneous (scratch, puncture, or prick) testing for non-venom, non-drug allergens, billed at one unit per allergen tested.
Does immunotherapy administration require a separate code from antigen preparation?
Yes. CPT 95165 covers antigen preparation, billed per 1cc dose, while 95115 or 95117 covers the injection administration itself.
Why do pediatric allergic rhinitis claims deny more often than adult claims?
Pediatric claims face stricter age-based testing thresholds, mandatory guardian-consent documentation for immunotherapy, and closer payer scrutiny on modifier 25 use during combined well-visit and sick-visit encounters.
How often should a payer require reassessment for continued pediatric immunotherapy?
Most payers require documented medical necessity reassessment every 12 months to justify continued allergen immunotherapy in pediatric patients.






