

Neurosurgery CPT codes document surgical procedures performed on the brain, spine, and peripheral nerves today. The American Medical Association maintains the CPT code set used across all US healthcare billing. This CPT code set differs entirely from the diagnosis codes coders use under ICD-10-CM daily.
CMS updates its National Correct Coding Initiative edits every calendar quarter. Version 32.2 took effect July 1, 2026, and version 32.3 takes effect October 1, 2026. Together, these two organizations govern how every neurosurgery procedure gets billed and reimbursed correctly nationwide.
Missing modifiers or improperly bundled codes remain leading causes of neurosurgery claim denials nationwide today. This guide breaks down every major neurosurgery CPT code family for coders and billers nationwide.

What Are Neurosurgery CPT Codes?
Neurosurgery CPT codes are five-digit numeric codes describing specific brain and spine procedures performed surgically. These codes fall under Category I, the most commonly reported CPT code classification used today. CPT codes describe the surgical procedure performed, not the underlying diagnosis treated by neurosurgeons daily.
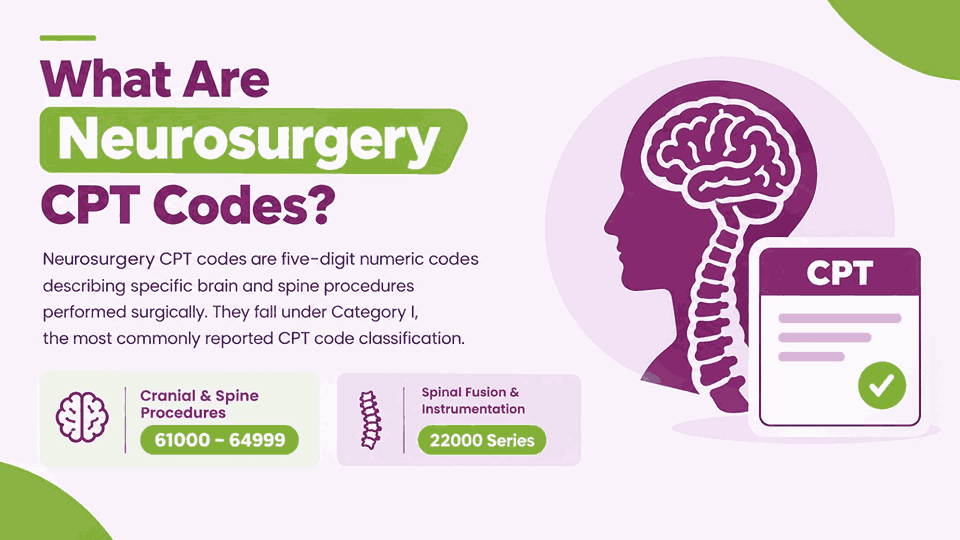
Neurosurgery CPT codes span mainly the 61000 through 64999 range for cranial and spine work. Spinal fusion and instrumentation codes instead sit within the separate 22000 series entirely for coders. The AAPC lists these code ranges among its core neurosurgery coding resources for coders nationwide. Together, these ranges define the complete neurosurgery CPT code landscape covered throughout this entire guide.
How Neurosurgery CPT Coding Works
Neurosurgery CPT coding follows a consistent four-step workflow from documentation review through final code linkage. Coders should never rely on procedure titles or physician shorthand phrases alone. Following each step in order reduces denials and supports accurate neurosurgery CPT code selection.
Start With the Operative Note
The operative note serves as the single most important document driving CPT code selection. It records the surgical approach, anatomical site, and every technique the surgeon used. Coders should read the entire note before selecting any preliminary neurosurgery CPT code. Skipping ahead to code lookup tools often produces incomplete or inaccurate procedure documentation.
Identify the Primary Procedure
The primary procedure represents the most significant, resource-intensive service performed during that surgical session. Secondary or bundled procedures typically require separate identification before any additional codes apply. Misidentifying the primary procedure often causes coders to bill add-on codes incorrectly.
Check Code-Specific Guidelines
Every CPT code carries specific guidelines published directly within the official AMA CPT codebook itself. These guidelines clarify bundled components, required documentation elements, and appropriate modifier usage. Coders should never assume two similar-sounding codes share identical billing rules or requirements.
Link CPT to ICD-10-CM
Every neurosurgery CPT code requires a supporting ICD-10-CM diagnosis code establishing medical necessity clearly. Payers deny claims where the diagnosis code fails to justify the procedure performed. This linkage step connects your CPT coding workflow directly to our Neurosurgery ICD-10 coding guide, which covers the diagnosis codes that support medical necessity.
What Are the Most Common Neurosurgery CPT Codes?
Neurosurgery CPT codes span brain, spine, and peripheral nerve procedures across several distinct code families. The table below previews the most frequently billed neurosurgery CPT codes overall. Later sections in this guide expand each code family with full documentation guidance.
| Neurosurgery Procedure | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Lumbar Discectomy | 63030, 63042 | Verify procedure type, spinal level, and documented surgical approach |
| Lumbar Laminectomy | 63047, 63048 | Distinguish primary decompression from additional-level services |
| Cervical Decompression | 63001, 63045, 63048 | Confirm spinal region and separately reportable additional levels |
| Cervical Fusion | 22551, 22552 | Verify approach, interspaces, and documented fusion services |
| Lumbar Fusion | 22612, 22630, 22633, 22634 | Identify fusion technique, approach, and additional procedures |
| Spinal Instrumentation | 22840–22847 | Verify instrumentation type and number of treated vertebral segments |
| Interbody Device | 22853, 22854 | Confirm device placement and applicable fusion documentation |
| Bone Grafting | 20930, 20931, 20936–20938 | Review graft source and documentation supporting separately reportable services |
| VP Shunt Procedures | 62223, 62230 | Distinguish initial placement from revision or replacement procedures |
| Intraoperative Neuromonitoring | 95940, 95941 | Verify monitoring documentation, personnel, timing, and applicable payer requirements |
These codes represent examples rather than a complete list of neurosurgical CPT codes used nationwide. The AMA CPT code set remains the authoritative source for current CPT code reporting requirements.
Spine Surgery CPT Codes
Spine procedures generate the highest reported billing volume among all neurosurgery CPT codes nationwide. This section covers every major lumbar, cervical, and thoracic spine procedure code family.
Lumbar Discectomy and Laminotomy CPT Codes
Lumbar discectomy and laminotomy procedures relieve nerve compression caused by displaced or degenerative disc material. Coding depends upon the treated interspace, surgical approach, laterality, and whether previous surgery occurred. Operative documentation should clearly distinguish primary procedures from revision procedures and additional treated interspaces.
| CPT Code | Description |
|---|---|
| 63030 | Laminotomy with discectomy, single lumbar interspace |
| 63035 | Each additional lumbar interspace, add-on code |
| 63042 | Reoperation laminotomy with discectomy, single lumbar interspace |
Coders should verify spinal level, laterality, interspace, and revision status before selecting applicable procedure codes.
Lumbar Laminectomy CPT Codes
Lumbar laminectomy provides spinal decompression by removing posterior vertebral structures surrounding affected neural elements. The operative note should identify every decompressed segment and the specific anatomical structures addressed surgically. Coders should distinguish laminectomy-based decompression from procedures involving separate disc removal or other techniques.
| CPT Code | Description |
|---|---|
| 63047 | Laminectomy, single lumbar vertebral segment |
| 63048 | Each additional lumbar vertebral segment, add-on code |
Documentation should establish each treated segment and support separate reporting when multiple procedures occur.
Cervical and Thoracic Decompression CPT Codes
Cervical and thoracic decompression procedures relieve pressure affecting spinal cords, nerve roots, or surrounding structures. Coding requires careful identification of spinal region, operative technique, treated levels, and decompression extent. Operative documentation should clearly distinguish cervical procedures from thoracic procedures performed during complex surgical encounters.
| CPT Code | Description |
|---|---|
| 63001 | Laminectomy with decompression, without facetectomy, foraminotomy, or discectomy, 1 or 2 vertebral segments, cervical |
| 63045 | Laminectomy, facetectomy, and foraminotomy, single vertebral segment, cervical |
| 63046 | Laminectomy, thoracic region, single segment |
| 63048 | Each additional vertebral segment, add-on code |
Coders should verify anatomical region and treated levels before reporting cervical or thoracic decompression services.
Cervical Fusion CPT Codes
Cervical fusion stabilizes affected vertebral segments by joining adjacent structures through surgical arthrodesis techniques. Coding considerations include surgical approach, interspace involvement, discectomy, decompression, instrumentation, and documented fusion services. The operative report should clearly establish which cervical levels received fusion during surgery.
| CPT Code | Description |
|---|---|
| 22551 | Anterior cervical discectomy and fusion, single interspace |
| 22552 | Each additional cervical interspace, add-on code |
Documentation should identify approach, fused interspaces, discectomy, arthrodesis, and associated instrumentation when applicable.
Lumbar Fusion CPT Codes
Lumbar fusion stabilizes spinal segments by creating permanent bony connections between adjacent vertebral structures. Coding considerations include surgical approach, fusion technique, treated levels, decompression, and interbody components. Operative documentation should clearly establish every fusion method performed during the surgical encounter.
| CPT Code | Description |
|---|---|
| 22612 | Posterior or posterolateral lumbar fusion, single level |
| 22630 | Posterior interbody lumbar fusion, single interspace |
| 22633 | Combined posterolateral and interbody lumbar fusion |
| 22634 | Each additional interspace, add-on code |
Coders should verify the documented fusion technique before assigning applicable lumbar arthrodesis procedure codes.
TLIF, PLIF, ALIF and Interbody Fusion
TLIF, PLIF, and ALIF describe different surgical pathways for achieving lumbar interbody spinal fusion. These approaches involve different anatomical routes, positioning considerations, and operative techniques for accessing disc spaces. Coders should focus on documented procedures rather than treating approach terminology as standalone CPT categories.
| Approach | Coding Focus |
|---|---|
| TLIF | Transforaminal lumbar interbody fusion technique |
| PLIF | Posterior lumbar interbody fusion technique |
| ALIF | Anterior lumbar interbody fusion technique |
| Interbody fusion | Fusion technique, level, approach, and device documentation |
Complete operative documentation should connect the surgical approach with the actual fusion services performed.
Spinal Instrumentation CPT Codes
Spinal instrumentation supports vertebral stabilization through hardware placed during qualifying fusion and reconstruction procedures. Coding depends upon fixation configuration, surgical approach, and the number of treated vertebral segments. Documentation should identify hardware placement clearly and distinguish segmental from non-segmental instrumentation.
| CPT Code | Description |
|---|---|
| 22840 | Posterior non-segmental instrumentation |
| 22842 | Posterior segmental instrumentation, 3–6 vertebral segments |
| 22843 | Posterior segmental instrumentation, 7–12 vertebral segments |
| 22845 | Anterior instrumentation, 2–3 vertebral segments |
| 22847 | Anterior instrumentation, 8 or more vertebral segments |
Coders should verify fixation type, approach, and vertebral segment count before reporting instrumentation services.
Interbody Devices CPT Codes
Interbody devices maintain disc-space height while supporting structural stability during spinal fusion procedures. Coding considerations include device placement, interspace involvement, fixation characteristics, and associated fusion documentation. Coders should verify whether device components remain separately reportable under applicable NCCI and payer policies.
| CPT Code | Description |
|---|---|
| 22853 | Interbody device with integral anterior instrumentation, placed in the disc space with interbody arthrodesis, each interspace |
| 22854 | Interbody device with integral anterior instrumentation, placed in a vertebral corpectomy defect with interbody arthrodesis, each contiguous defect |
Bone Grafts CPT Codes in Spine Surgery
Bone grafting supports spinal fusion by providing material that promotes structural healing between treated vertebral segments. Coding considerations include graft source, graft type, preparation, and whether harvesting occurred separately. Operative documentation should clearly identify graft material and its specific role during spinal reconstruction.
| CPT Code | Description |
|---|---|
| 20930 | Allograft, morselized, spine surgery |
| 20931 | Allograft, structural, spine surgery |
| 20936 | Autograft, local, spine surgery |
| 20937 | Autograft, morselized, additional site |
| 20938 | Autograft, structural, additional site |
Coders should verify graft source and documentation before reporting applicable bone graft services.
Cranial and Brain Surgery CPT Codes
Cranial surgery CPT codes cover procedures treating brain disorders, injuries, tumors, bleeding, and vascular abnormalities. Accurate coding requires operative documentation describing anatomy, surgical approach, treatment purpose, and procedural extent. Coders should distinguish therapeutic procedures from diagnostic services, especially during complex intracranial surgical encounters.
Craniotomy and Craniectomy
Cranial surgery CPT codes cover procedures treating brain disorders, injuries, tumors, bleeding, and vascular abnormalities. Accurate coding requires operative documentation describing anatomy, surgical approach, treatment purpose, and procedural extent. Coders should distinguish therapeutic procedures from diagnostic services, especially during complex intracranial surgical encounters.
| Procedure | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Craniotomy | 61304–61548 | Verify surgical purpose, anatomical site, approach, and documented extent |
| Craniectomy | 61500–61576 | Confirm bone removal, treated region, and reconstruction requirements |
| Cranial Reconstruction | 62140–62143 | Verify defect size, reconstruction method, and documented materials |
Brain Tumor Removal
Brain tumor procedures remove abnormal intracranial tissue while preserving surrounding neurological structures whenever possible. Coding depends upon tumor location, surgical approach, anatomical complexity, and documented extent of resection. Operative documentation should establish the treated brain region and distinguish tumor removal from diagnostic biopsy.
| Procedure | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Supratentorial Tumor Excision | 61510–61512 | Verify tumor location and documented resection approach |
| Infratentorial Tumor Excision | 61518–61521 | Confirm posterior fossa location and operative approach |
| Intracranial Biopsy | 61500-series applicable codes | Verify biopsy purpose, location, and surgical technique |
Intracranial Hemorrhage Procedures
Intracranial hemorrhage procedures address bleeding occurring within or around intracranial structures. Coding considerations include hemorrhage location, surgical evacuation method, approach, and documented procedural objectives. Operative reports should distinguish hematoma evacuation from craniotomy performed for another underlying condition.
| Procedure | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Intracranial Hematoma Evacuation | 61312–61315 | Verify hematoma location, approach, and evacuation method |
| Subdural Hematoma Treatment | 61312, 61314 | Confirm hematoma type and documented surgical intervention |
| Epidural Hematoma Treatment | 61314–61315 | Verify location and operative evacuation technique |
Cerebral Aneurysm Procedures
Cerebral aneurysm procedures treat abnormal arterial dilations that can rupture or cause neurological complications. Coding depends upon aneurysm location, surgical technique, vascular access, and documented treatment approach. Operative documentation should distinguish open aneurysm clipping from endovascular treatment performed through catheter-based techniques.
| Procedure | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Aneurysm Clipping | 61697–61703 | Verify aneurysm location, approach, and clipping technique |
| Endovascular Aneurysm Treatment | 61624–61626 | Confirm central nervous system vessel and technique (61626 is for non-CNS head and neck vessels) |
| Endovascular Vasospasm Treatment | 61650–61651 | Verify drug infusion documentation and vascular territories |
Stereotactic Neurosurgery
Stereotactic neurosurgery uses precise three-dimensional targeting to reach specific intracranial structures. These procedures commonly support lesion biopsy, ablation, stimulation, or focused therapeutic interventions. Coding requires documentation of targeting methods, treated structures, guidance techniques, and therapeutic objectives.
| Procedure | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Stereotactic Biopsy | 61720–61721 | Verify lesion location and stereotactic guidance documentation |
| Stereotactic Radiosurgery | 61796–61800 | Confirm treatment planning and documented radiation delivery |
| Stereotactic Procedures | 61720-series | Verify targeting technique and treated intracranial structure |
Hydrocephalus and CSF Shunt CPT Codes
CSF shunt procedures divert excess cerebrospinal fluid away from the ventricular system surgically. These CPT codes cover shunt placement, revision, removal, and documented complication management.
VP Shunt Placement
Ventriculoperitoneal shunt placement diverts cerebrospinal fluid from cerebral ventricles into the peritoneal cavity. Coding considerations include ventricular catheter placement, distal catheter placement, valve components, and surgical approach. Documentation should establish hydrocephalus treatment, shunt configuration, and complete operative services performed during placement.
| CPT Code | Description | Key Coding Consideration |
|---|---|---|
| 62223 | Creation of shunt; ventriculo-peritoneal | Verify ventricular and peritoneal catheter placement |
| 62225 | Replacement or irrigation of ventricular catheter | Confirm ventricular catheter involvement |
| 62230 | Replacement or revision of CSF shunt | Verify shunt component revision or replacement |
Shunt Revision and Replacement
Shunt revision procedures correct malfunctioning, displaced, obstructed, or otherwise compromised cerebrospinal fluid diversion systems. Coding depends upon the specific component revised, replaced, or repositioned during surgery. Operative documentation should identify each affected component and explain the reason for surgical revision.
| Procedure | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Ventricular Catheter Revision | 62225 | Confirm ventricular catheter involvement |
| CSF Shunt Revision | 62230 | Identify revised or replaced shunt components |
| Shunt System Replacement | 62230 | Verify replacement extent and documented surgical purpose |
Shunt Removal
Complete shunt system removal is reported with 62256 (without replacement) or 62258 (with replacement). Coding depends upon which shunt components require removal and the documented surgical approach. Operative documentation should distinguish complete system removal from removal involving individual shunt components.
| Procedure | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Complete System Removal, No Replacement | 62256 | Verify the entire system was removed |
| Complete System Removal with Replacement | 62258 | Confirm removal and replacement in the same operation |
Shunt Complications
CSF shunt complications include obstruction, infection, displacement, malfunction, overdrainage, and underdrainage. These conditions generally require coding the corrective procedure alongside the documented complication diagnosis. Operative documentation should identify the malfunctioning component and corrective intervention performed during surgery.
| Shunt Complication | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Shunt Obstruction | 62230 | Verify shunt revision or replacement performed |
| Shunt Infection | 62256 or 62258 | Confirm complete system removal, with or without replacement |
| Shunt Malfunction | 62230 | Document malfunction and corrective shunt procedure |
| Ventricular Catheter Malfunction | 62225 | Verify ventricular catheter revision or replacement |
| Shunt Displacement | 62230 | Confirm displaced component and corrective intervention |
| Shunt Overdrainage | 62230 | Verify documented shunt revision or replacement |
Neurostimulator and Functional Neurosurgery CPT Codes
Functional neurosurgery CPT codes cover procedures using implanted devices for targeted neurological conditions. These procedures include deep brain stimulation, electrode placement, neurostimulator implantation, and device management.
Deep Brain Stimulation
Deep brain stimulation uses implanted electrodes to modulate specific brain regions through controlled electrical stimulation. This treatment commonly supports movement disorder management involving carefully selected neurological conditions. Coding requires documentation identifying targeted brain structures, surgical approach, and implanted stimulation system components.
| Procedure | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Intracranial Neurostimulator Electrode Placement | 61863, 61864 | Verify targeted brain structure and electrode implantation technique |
| Additional Electrode Placement | 61867, 61868 | Confirm multiple electrode placement and documented surgical approach |
| Pulse Generator Implantation | 61885, 61886 | Verify generator type, location, and implantation documentation |
Coders should distinguish electrode implantation from pulse generator placement during staged deep brain stimulation procedures.
Electrode Implantation
Electrode implantation places stimulation leads within specific neurological structures for therapeutic electrical modulation. Documentation should establish electrode location, implantation technique, laterality, and whether multiple leads were implanted. Coders should distinguish intracranial electrodes from peripheral or spinal neurostimulation leads during reporting.
| Procedure | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Single Intracranial Electrode | 61863 | Verify unilateral electrode implantation and targeted brain structure |
| Multiple Intracranial Electrodes | 61867 | Confirm multiple electrode placement and documented targeting |
| Electrode Revision | 61880 | Verify revision, replacement, or repositioning of implanted electrodes |
Device location and implantation stage remain important considerations for accurate functional neurosurgery coding.
Neurostimulator Procedures
Neurostimulator procedures include implantation, replacement, revision, and removal of stimulation system components. Coding depends upon the specific component treated and documented procedural purpose. Operative documentation should identify generators, leads, electrodes, revisions, replacements, and anatomical implantation sites.
| Procedure | Representative CPT Codes | Key Coding Consideration |
|---|---|---|
| Neurostimulator Generator Implantation | 61885, 61886 | Verify generator type and anatomical implantation location |
| Neurostimulator Component Replacement | 61885, 61886 | Confirm replaced component and documented procedural purpose |
| Electrode Revision | 61880 | Verify lead or electrode revision and surgical approach |
| Neurostimulator Removal | 61880 | Confirm removed component and complete operative documentation |
Coders should verify device components carefully because functional neurosurgery often involves multiple staged procedures.
Intraoperative Neuromonitoring CPT Codes
Intraoperative neuromonitoring tracks neurological function throughout complex spine and cranial surgical procedures. Monitoring can help identify neurological changes requiring immediate surgical attention during procedures. Coding requires documentation of monitoring type, qualified personnel, surgical duration, and medical necessity.
| CPT Code | Description | Key Coding Consideration |
|---|---|---|
| 95940 | Continuous intraoperative neurophysiology monitoring in the operating room, one-on-one, each 15 minutes | Verify monitoring time and personal attendance |
| 95941 | Continuous intraoperative neurophysiology monitoring, remote or multi-case, per hour | Document monitoring time and remote setup |
| G0453 | Medicare remote monitoring dedicated to one patient, each 15 minutes | Use instead of 95941 for Medicare claims |
The operating surgeon cannot report neuromonitoring performed during their own surgery.
What Are Neurosurgery CPT Add-On Codes?
Neurosurgery add-on codes report qualifying services performed alongside designated primary procedures. These codes commonly apply when additional spinal levels or related services receive separate reporting. Understanding add-on coding prevents incorrect billing, missed services, and inappropriate primary procedure reporting.
What Are Add-On Codes?
Add-on CPT codes describe additional services performed alongside an eligible primary procedure. These codes cannot generally stand alone without an associated qualifying primary procedure. Coders should review CPT guidelines carefully before reporting any add-on service separately.
| Add-On Code | Description | Key Coding Consideration |
|---|---|---|
| 63048 | Each additional lumbar vertebral segment | Requires qualifying primary decompression procedure |
| 63035 | Each additional lumbar interspace | Requires qualifying primary laminotomy with discectomy |
| 22552 | Each additional cervical interspace | Requires qualifying primary cervical fusion procedure |
| 22634 | Each additional lumbar interspace | Requires qualifying combined lumbar fusion procedure |
Add-on codes generally receive separate reporting without modifier 51 when CPT guidelines permit.
Common Spine Add-On Codes
Spine surgery frequently uses add-on codes for additional decompressed or fused anatomical levels. These services extend the primary procedure across additional documented vertebral segments or interspaces. Coders should verify contiguous levels and supporting operative documentation before reporting additional services.
| CPT Code | Associated Procedure | Coding Focus |
|---|---|---|
| 63035 | Lumbar laminotomy with discectomy | Additional lumbar interspace |
| 63048 | Lumbar decompression | Additional vertebral segment |
| 22552 | Cervical fusion | Additional cervical interspace |
| 22634 | Combined lumbar fusion | Additional lumbar interspace |
Documentation should clearly identify each additional level receiving the qualifying surgical service.
Add-On Coding Rules
Add-on coding rules determine when additional services qualify for separate CPT reporting. Coders must confirm the primary procedure appears alongside each applicable add-on service. NCCI edits, CPT guidelines, and payer policies should remain part of every coding review.
| Coding Rule | Application |
|---|---|
| Primary Procedure Required | Report add-on services only with qualifying primary procedures |
| No Standalone Reporting | Add-on codes generally cannot replace primary procedure codes |
| Multiple Levels | Document every additional treated level clearly |
| Modifier 51 | Most designated add-on codes remain exempt from modifier 51 |
| NCCI Review | Check applicable edits before submitting claims |
Correct add-on coding requires matching operative documentation with current CPT reporting requirements and payer policies.
What Are the Key CPT Modifiers for Neurosurgery?
Neurosurgery modifiers clarify circumstances surrounding a reported procedure without changing its core CPT code. Missing or misapplied modifiers remain a frequent cause of neurosurgery claim denials nationwide. This section explains each modifier commonly used across cranial, spine, and functional neurosurgery procedures.
Modifier 22
Modifier 22 reports increased procedural complexity beyond what the base CPT code describes. Documentation must clearly justify additional time, difficulty, or unusual intraoperative circumstances. Payers routinely request operative notes before approving any claim using modifier 22.
Modifier 24
Modifier 24 reports an unrelated evaluation and management service during a postoperative global period. This modifier applies only when the visit addresses a condition unrelated entirely. Documentation should clearly separate the unrelated diagnosis from the original surgical condition treated.
Modifier 25
Modifier 25 reports a significant, separately identifiable evaluation and management service by the same physician on the day of a procedure or other service. The service may relate to the procedure, but it must go beyond the usual preoperative work the procedure already includes. When the visit results in the decision for major surgery, use modifier 57 instead.
Modifier 50
Modifier 50 reports a bilateral procedure performed identically on both sides during surgery. Neurosurgery examples include bilateral nerve decompression or bilateral instrumentation placement during spine surgery. Documentation should confirm both sides received the identical, separately identifiable surgical treatment.
Modifier 59 and X{E/S/P/U}
Modifier 59 reports a distinct procedural service not normally reported together under NCCI edits. The X-modifiers, XE, XS, XP, and XU, replace modifier 59 with greater specificity today. CMS prefers these specific X-modifiers whenever documentation supports their more precise application.
| Modifier | Meaning |
|---|---|
| 59 | Distinct procedural service |
| XE | Separate encounter |
| XS | Separate structure |
| XP | Separate practitioner |
| XU | Unusual, non-overlapping service |
Modifiers 62 and 66
Modifier 62 reports two surgeons performing distinct portions of one single surgical procedure. Modifier 66 reports a surgical team involving more than two operating physicians. Each co-surgeon or team member must submit separate, individually documented operative reports.
Global Surgery Modifiers
Global surgery modifiers, including 57, 58, 78, and 79, address care during postoperative periods. These modifiers determine whether additional services receive separate payment beyond the global surgical package. The next section explains each global period and its associated modifier requirements fully.
How Do NCCI Edits Impact Neurosurgery Billing?
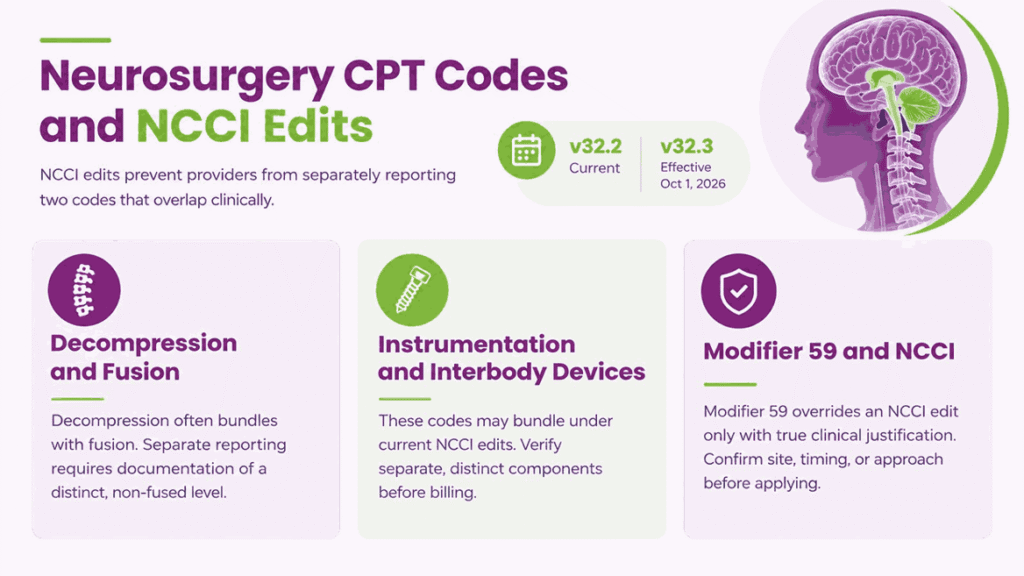
NCCI edits prevent providers from separately reporting two codes that overlap clinically. CMS updates these edits quarterly, with version 32.2 currently governing claims and version 32.3 taking effect October 1, 2026.
Understanding common neurosurgery bundling pairs helps coders avoid frequent, preventable claim denials. For a full walkthrough of how these edits fit into the claims process, see our neurosurgery medical billing guide.
Decompression and Fusion
Decompression codes often bundle automatically with fusion codes performed during the same session. NCCI treats decompression as an included component whenever fusion addresses the identical spinal level. Separate reporting requires documentation showing decompression at a distinct, non-fused anatomical level.
Instrumentation and Interbody Devices
Instrumentation codes frequently bundle with certain interbody device codes under current NCCI edit pairs. Documentation must establish that both services represent genuinely separate, distinct surgical components performed. Coders should verify current edit tables before assuming any instrumentation-device pairing remains billable.
Modifier 59 and NCCI
Modifier 59 overrides an NCCI edit only when documentation supports a truly distinct service. Appending modifier 59 automatically, without genuine clinical justification, constitutes improper unbundling under CMS guidelines. Coders should confirm anatomical site, session timing, or approach before applying this override.
What Are Neurosurgery CPT Global Periods?
The global surgery period defines a fixed window of bundled postoperative care following surgery. CMS assigns every neurosurgery CPT code one of three global period lengths. Understanding these periods prevents billing separately for services already bundled into payment.
000-Day Global
A 000-day global period includes only the day of surgery itself, without additional coverage. Minor procedures like certain injections or simple aspirations typically carry this shortest global period. Any related service performed the next day becomes separately billable under this classification.
010-Day Global
A 010-day global period bundles the surgery date plus nine additional postoperative recovery days. Some neurosurgery procedures involving minor decompression or simple hardware removal fall under this period. Related visits occurring within those ten days remain included, not separately billable.
090-Day Global
A 090-day global period covers the day before surgery, the day of surgery, and the ninety days that immediately follow. Most major neurosurgery procedures, including craniotomy and spinal fusion, carry this longest period. Related complications or routine follow-up visits during those days remain bundled entirely.
Postoperative Visits
Postoperative visits evaluate recovery, healing, complications, neurological status, and treatment progress after surgery. Routine related visits generally remain bundled when performed during applicable global periods. Separate reporting requires documentation supporting an exception under Medicare or applicable payer guidelines.
| Visit Circumstance | Coding Treatment | Documentation Focus |
|---|---|---|
| Routine Postoperative care | Usually included | Recovery and surgical follow-up |
| Unrelated Condition | Potentially separately reportable | Distinct diagnosis and medical necessity |
| Complication Management | May require separate reporting | Complication and treatment documentation |
| Staged Procedure | Potentially separately reportable | Planned subsequent surgical service |
Coders should review postoperative documentation carefully before assigning separate evaluation and management services.
Global Period Modifiers
Global surgery modifiers identify circumstances requiring separate reporting during an applicable postoperative global period. Common modifiers include 24, 25, 57, 58, 78, and 79 for different circumstances. Correct modifier selection requires documentation supporting the specific relationship between services and original surgery.
| Modifier | Application | Global Period Context |
|---|---|---|
| 24 | Unrelated E/M service | Separate condition during postoperative period |
| 25 | Significant separate E/M service | Distinct E/M service accompanying another procedure |
| 57 | Decision for major surgery | Surgical decision during qualifying E/M encounter |
| 58 | Staged or related procedure | Planned subsequent procedure during global period |
| 78 | Unplanned return to operating room | Related postoperative complication |
| 79 | Unrelated procedure | Separate procedure during global period |
Medicare global surgery rules should remain the primary reference when determining modifier applicability.
How to Choose the Correct Neurosurgery CPT Code
Choosing the correct neurosurgery CPT code follows a repeatable seven-step decision framework consistently. This structured approach reduces coding errors, prevents denials, and supports accurate claim submission overall.
Step 1: Identify the Procedure Performed
Start by identifying exactly what surgical procedure the operative note actually describes. Avoid relying on procedure titles alone, since documentation details often differ significantly.
Step 2: Identify the Anatomical Region
Confirm whether the procedure involved cranial, cervical, thoracic, lumbar, or peripheral nerve anatomy specifically. Anatomical region alone often determines which entire code family applies correctly here.
Step 3: Identify the Surgical Approach
Determine whether the surgeon used an anterior, posterior, lateral, or endoscopic surgical approach here. Approach frequently changes the applicable CPT code even when anatomy remains identical.
Step 4: Identify the Level or Number of Levels
Count every treated vertebral segment, interspace, or anatomical level documented within the operative note. Additional levels typically require separate add-on codes beyond the primary procedure code.
Step 5: Identify Additional Procedures and Devices
Review the note for instrumentation, interbody devices, bone grafts, or other separately reportable services performed. Each additional service may require its own distinct, separately reportable CPT code.
Step 6: Check Bundling and NCCI Edits
Verify whether any identified codes bundle together under current CMS National Correct Coding Initiative edits. Documentation must support any modifier used to override a legitimate bundling edit.
Step 7: Apply Appropriate Modifiers and Verify Documentation
Apply modifiers only when documentation genuinely supports increased complexity, distinct services, or bilateral treatment. Final code selection should always match the complete, verified operative documentation exactly.
What Are Common Neurosurgery CPT Coding Errors?
Neurosurgery claims often involve complex procedures requiring precise documentation and careful CPT code selection. The following errors commonly create denials, payment delays, bundling issues, and inaccurate reimbursement:
- Incorrect Procedure Selection: Coders select CPT codes without reviewing the complete operative report carefully. Always verify anatomy, approach, technique, and documented surgical services before selecting codes.
- Missing Additional Levels: Coders overlook additional spinal levels documented within complex decompression procedures. Review operative reports carefully for every separately reportable additional treated level.
- Incorrect Modifier Usage: Incorrect modifiers can trigger NCCI edits, claim denials, and reimbursement delays. Match each modifier with documented circumstances and current CMS reporting requirements.
- Unbundling Procedures: Coders separately report services already included within comprehensive neurosurgery procedures. Check NCCI edits before reporting bundled components separately on claims.
- Incorrect Global Period Reporting: Postoperative services may be incorrectly billed during applicable global surgery periods. Verify global indicators before reporting postoperative E/M services separately from surgical reimbursement.
Practices that face recurring denials often work with specialized neurosurgery billing services to keep coding, modifier use, and claim follow-up accurate.
Frequently Asked Questions About Neurosurgery CPT Codes
What Are Neurosurgery CPT Codes?
Neurosurgery CPT codes identify procedures performed on the brain, spine, and peripheral nerves. They describe procedures and services, while ICD-10-CM codes describe diagnoses supporting medical necessity.
How Do NCCI Edits Affect Neurosurgery CPT Coding?
NCCI edits identify code combinations that may represent incorrect or overlapping procedural reporting. CMS requires appropriate documentation before modifiers bypass applicable edits under qualifying clinical circumstances.
What Are Neurosurgery CPT Add-On Codes?
Add-on CPT codes report qualifying additional services performed with designated primary procedures appropriately. They generally cannot stand alone and require qualifying primary procedures documented for reporting.
How Do Global Periods Affect Neurosurgery CPT Billing?
Global periods bundle specified postoperative services into payment for applicable neurosurgical procedures postoperatively. Separate reporting requires qualifying circumstances, modifiers, and documentation supporting services beyond bundled care.
Which Documentation Supports Accurate Neurosurgery CPT Coding?
Operative notes should document anatomy, approach, levels, techniques, devices, findings, and procedures performed. Complete documentation helps coders select CPT codes and support medical necessity for claims.






