The Louisa Carman Medical Debt Relief Act rewrote how New Jersey providers collect self-pay balances. It sits at N.J.S.A. 56:11-56 et seq. and reaches every physician practice, surgery center, and hospital in the state.
Most coverage of this law was written for patients or for defense counsel. Very little of it explains what changes inside an accounts receivable workflow on Monday morning.
That gap matters right now. On August 10, 2026, a federal court held that the Fair Credit Reporting Act preempts a state medical debt reporting ban. The ruling came out of Texas, but it puts pressure on New Jersey’s credit reporting provision.
This guide covers what the Act requires, which provisions face preemption risk and which do not, how the rules change AR workflow, and what penalties apply.
What Is the Louisa Carman Medical Debt Relief Act?
The Louisa Carman Medical Debt Relief Act is a New Jersey law regulating how medical debt is reported, billed, and collected. Governor Phil Murphy signed it on July 22, 2024 as A3861 and S2806, enacted as P.L.2024, c.48.
The law is named for Louisa Carman, a Murphy administration staffer who drafted it before her death in January 2024. Senators Shirley Turner and Teresa Ruiz sponsored the Senate companion bill.
Key statutory facts:
- Codified at N.J.S.A. 56:11-56 through 56:11-63
- Supplements the New Jersey Fair Credit Reporting Act at N.J.S.A. 56:11-28 et seq.
- Contains an express severability clause at Section 8
- Enforced solely by the Office of the Attorney General
When Did Each Provision Take Effect?
The Act split its effective dates. Sections 3 and 7 became operative on the enactment date. Everything else activated one year later.
| Provision | Statute | Effective Date |
|---|---|---|
| Credit reporting ban | N.J.S.A. 56:11-58 | July 22, 2024 |
| Voided debt and penalties | N.J.S.A. 56:11-62 | July 22, 2024 |
| 120-day pre-collection hold | N.J.S.A. 56:11-59(a) | July 22, 2025 |
| 30-day advance notice | N.J.S.A. 56:11-59(b) | July 22, 2025 |
| Required disclosure language | N.J.S.A. 56:11-59(c) | July 22, 2025 |
| Debt sale restrictions | N.J.S.A. 56:11-59(d) | July 22, 2025 |
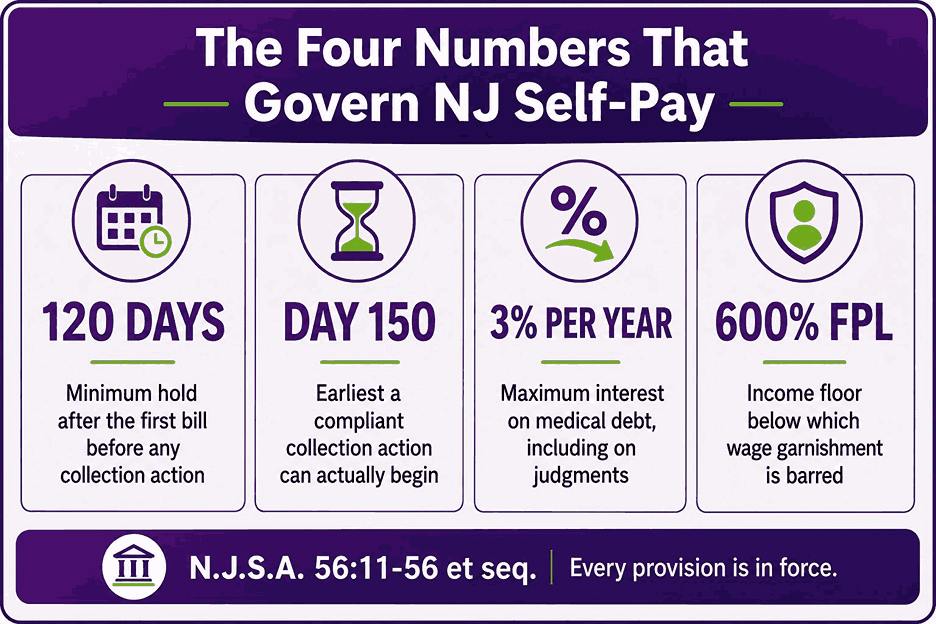
| 3% interest cap | N.J.S.A. 56:11-60(a) | July 22, 2025 |
| Wage garnishment ban | N.J.S.A. 56:11-60(b) | July 22, 2025 |
| Pending appeal freeze | N.J.S.A. 56:11-61 | July 22, 2025 |
All provisions are now in force. Any practice still running a pre-2024 collections workflow is out of compliance on at least four counts.
Who Counts as a Medical Creditor Under the Act?
A medical creditor is any person or entity that provides health care services and is owed money by a patient. The definition carries no size threshold and no small-practice carve-out.
Covered entities include:
- Physician practices, solo and group
- Ambulatory surgery centers
- Acute care hospitals and health systems
- Dental practices
- Laboratories, imaging centers, and medical transport providers
- Any health care professional licensed under Title 45
The Act also defines medical debt collectors and medical debt buyers separately. A debt buyer is treated as a medical debt collector for all purposes under the statute.
What Debt Falls Outside the Act?
Not every patient balance qualifies as medical debt. The statute excludes five categories, and the scope of the exclusions catches most practices by surprise.
| Excluded Category | Detail |
|---|---|
| Cosmetic procedures | Excluded from the definition of health care service entirely |
| General credit cards | Unless the card is issued solely for health care costs |
| Veterinary services | Excluded outright |
| Home equity or general lines of credit | Excluded outright |
| Retained insurance payments | Payments sent to the patient and kept |
| Secured debt | Excluded outright |
The cosmetic carve-out is the one most often missed. Dermatology and plastic surgery practices billing purely elective work sit outside the Act for those balances. Reconstructive surgery and dentistry remain covered.
What Does the Act Prohibit and Require?
The Act imposes six distinct obligations. Each one attaches to a different point in the revenue cycle, from statement generation through legal action.
What Are the Credit Reporting Restrictions?
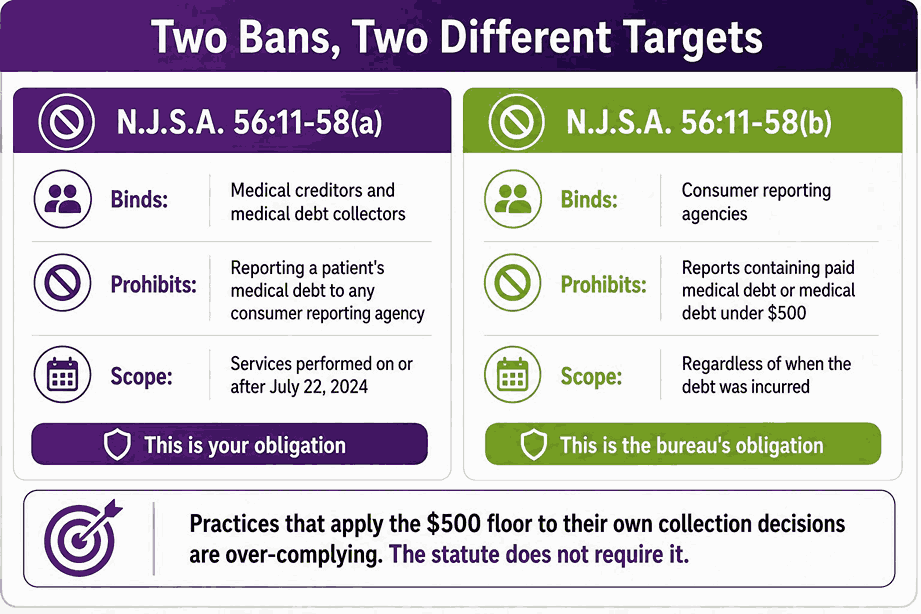
Medical creditors and medical debt collectors cannot report a patient’s medical debt to any consumer reporting agency for services performed on or after July 22, 2024.
A second restriction binds the credit bureaus rather than providers. Equifax, Experian, and TransUnion cannot include a patient’s paid medical debt or any medical debt under $500 in a consumer report, regardless of when it was incurred.
Practical distinction: the first rule is your obligation. The second is the bureau’s obligation. Confusing the two leads practices to over-apply the $500 floor to their own collection decisions, which the statute does not require.
How Long Must Providers Wait Before Collections?
No collection action may begin until 120 days after the first bill was sent and a reasonable payment plan has been offered. Both conditions must be satisfied. The clock alone is not enough.
A separate 30-day notice runs on top of that. At least 30 days before any collection action, the provider must send one additional bill plus a notice that identifies the specific collection actions planned and states a deadline no earlier than 30 days out.
In practice, the earliest a compliant collection action can start is day 150.
What Is Not a Collection Action Under the Act?
This is the most misread provision in the statute, and it costs practices real money. Routine billing is expressly excluded from the definition of collection action.
Permitted during the 120-day hold:
- Sending invoices and bills to the patient
- Sending reasonable reminders to pay an invoice or bill
- Collecting copayments, coinsurance, and deductibles at the point of service
Prohibited during the hold:
- Selling the patient’s debt to another party
- Reporting the patient to a consumer reporting agency
- Placing a lien on property or attaching a bank account
- Filing a civil action or garnishing wages
Many practices read the 120-day hold and suspend statementing entirely. That is over-compliance. You can and should keep billing throughout the hold period.
What Qualifies as a Reasonable Payment Plan?
The statute defines the term with six specific criteria. A plan that misses any one of them does not satisfy the offer requirement, which means the 120-day condition never clears.
| Criterion | Requirement |
|---|---|
| Monthly amount | Affordable to the patient, or no more than 3% of monthly income if known |
| Duration | A reasonable timeframe, including six months to five years |
| Adjustability | Must allow changes if the patient’s finances change materially |
| Documentation | Written agreement stating total owed, monthly amount, schedule, and interest |
| Grace period | At least 60 days for late payments |
| Interest | No more than 3% per annum |
Two further protections apply. A provider cannot pursue collection against a patient who accepts and complies with the plan. Acceptance is not an admission that the debt is valid, and the patient keeps all legal defenses.
What Is the Interest Rate Cap on Medical Debt?
Medical creditors and debt collectors cannot charge more than 3% per annum on medical debt. The cap extends to judgments. Interest on any judgment for medical debt is calculated under court rules but cannot exceed 3%.
When Is Wage Garnishment Prohibited?
Wage garnishment is barred for any patient with annual income below 600% of the federal poverty level. That threshold is high enough to cover most patient-pay populations in New Jersey.
Income screening is therefore a prerequisite to garnishment, not an optional step. A practice that garnishes without screening carries the full violation risk.
What Happens When an Insurance Appeal Is Pending?
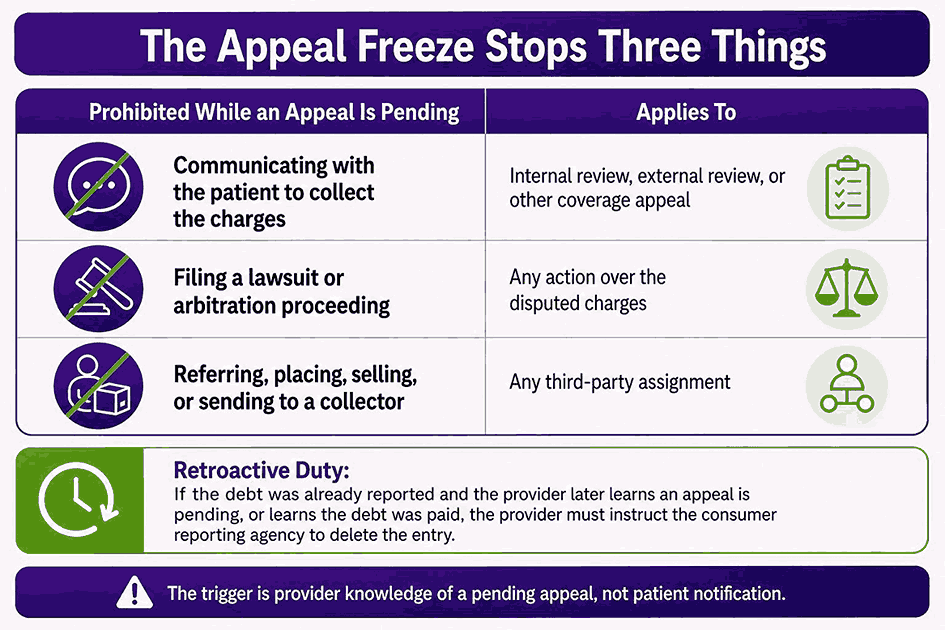
Section 6 imposes a hard freeze. If the provider knows an internal review, external review, or other appeal of a coverage decision is pending, three things become prohibited.
- Communicating with the patient to collect the charges
- Filing a lawsuit or arbitration proceeding over the charges
- Referring, placing, selling, or sending the debt to a collector
A retroactive duty also attaches. If the debt was already reported and the provider later learns of a pending appeal or learns the debt was paid, the provider must instruct the consumer reporting agency to delete the entry.
Is the NJ Credit Reporting Ban Still Enforceable in 2026?
Yes, as of August 2026 the New Jersey ban remains in force. No court has struck it down. But the legal position has moved materially in the past month and the risk is now concrete rather than theoretical.
What Did the August 2026 Texas Ruling Decide?
On August 10, 2026, Judge Robert Pitman of the Western District of Texas granted summary judgment in CDIA v. Paxton. The court held that the Fair Credit Reporting Act preempts the Texas medical debt reporting ban.
The Consumer Data Industry Association argued that FCRA Section 1681t(b)(1)(E) bars state laws that regulate the contents of a consumer report. The court agreed and found the Texas statute unenforceable.
This matters because it is the first actual holding on the question. The earlier Cornerstone Credit Union League v. CFPB decision from July 2025 contained preemption language, but that language was dicta rather than a ruling.
Does That Ruling Apply to New Jersey?
No. A Western District of Texas decision binds nothing in New Jersey. The state sits in the Third Circuit, which has issued no controlling precedent on FCRA preemption of medical debt reporting statutes.
Contrary authority also exists and is stronger on paper:
- CDIA v. Frey, 26 F.4th 1 (1st Cir. 2022) held a Maine medical debt reporting restriction was not preempted
- Aargon Agency v. O’Laughlin, 70 F.4th 1224 (9th Cir. 2023) read FCRA preemption narrowly as applied to furnishers
- Galper v. JPMorgan Chase, 802 F.3d 437 (2d Cir. 2015) reached a similar conclusion on furnisher-level state regulation
A circuit split is forming. Around fifteen states now restrict medical debt reporting, and New Jersey is one of them. The question will likely reach an appellate court before it reaches New Jersey directly.
Which Provisions Would Preemption Actually Reach?
This is the part almost nobody separates out, and it is the part that determines how much of your workflow is actually at risk. The preemption theory runs to the contents of consumer reports. It does not touch collection conduct.
| Provision | Preemption Exposure | Reason |
|---|---|---|
| Credit reporting ban (§3a) | High | Regulates furnishing to a consumer reporting agency |
| $500 and paid-debt bar (§3b) | High | Directly regulates consumer report contents |
| 120-day pre-collection hold | None | Governs collection timing, not credit reporting |
| 30-day advance notice | None | Governs notice content, not credit reporting |
| Reasonable payment plan mandate | None | Governs contract terms with the patient |
| 3% interest cap | None | Governs pricing of the debt |
| Wage garnishment ban | None | Governs judicial collection remedies |
| Debt sale restrictions | None | Governs assignment terms |
| Pending appeal freeze | Partial | Delete-on-notice duty touches reporting |
Section 8 of the Act makes this split operative. The severability clause states that if any provision is deemed unenforceable, the remaining provisions stay enforceable. The statute also directs courts to construe it liberally.
The practical read: if the credit reporting ban falls, roughly eighty percent of your operational obligations survive untouched. Planning as though a preemption ruling would void the whole Act is a mistake.
What Should Providers Do While Litigation Continues?
Operate as though the Act is fully enforceable, because in New Jersey it is. Four steps reduce exposure in either direction.
- Keep credit bureau reporting suppressed for all covered New Jersey medical debt
- Add indemnification language to collection agency contracts covering a preemption reversal
- Separate reporting controls from collection-conduct controls in your compliance documentation
- Track Third Circuit filings and any New Jersey Attorney General guidance
How Does the Act Change Your Revenue Cycle Workflow?
The Act converts several informal practices into legal prerequisites. Four areas of the revenue cycle need rebuilding, and none of them are configuration defaults in standard practice management systems.
How Should AR Aging Buckets Be Reconfigured?
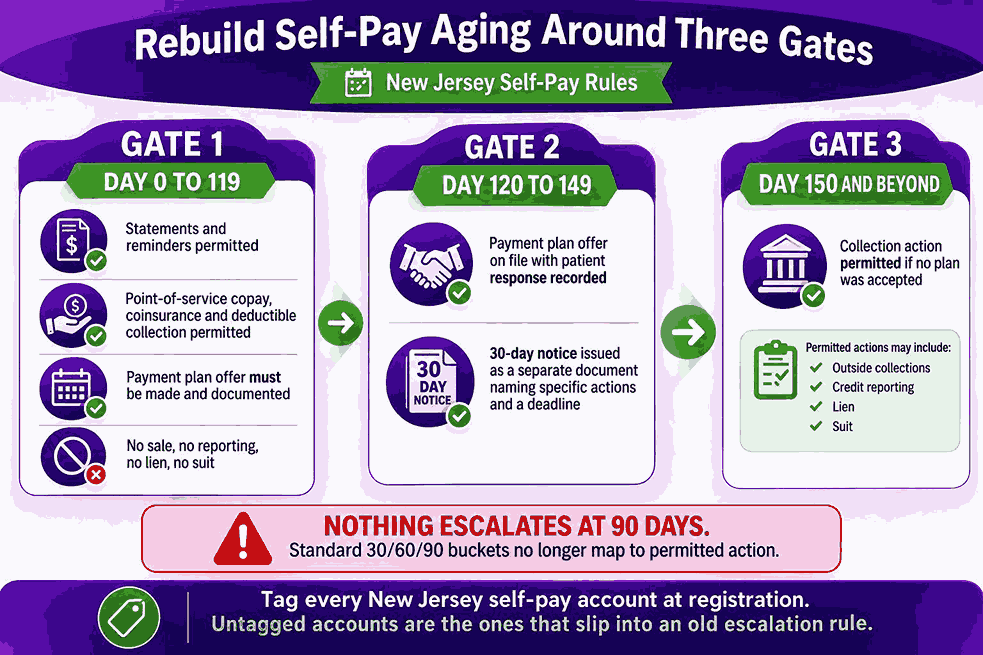
Standard 30, 60, and 90 day buckets no longer map to permitted action. Under the Act, nothing escalates at 90 days. The first decision point is day 120, and the first action point is day 150.
Rebuild self-pay aging around three gates:
- Day 0 to 119: statements and reminders only, payment plan offer must be documented
- Day 120 to 149: payment plan offered and 30-day notice issued
- Day 150 and beyond: collection action permitted if no plan was accepted
Tag every New Jersey self-pay account at registration. Accounts that never get tagged are the ones that slip into an old escalation rule.
What Changes in the Statement and Dunning Sequence?
Every collection communication must carry a specific disclosure. The statute requires a statement in at least 14-point boldface font confirming that the debt has not been reported to a consumer reporting agency, and that any reported portion is void.
The font size is not advisory. It is written into N.J.S.A. 56:11-59(c). Statement templates that carry the language in body copy do not comply.
The 30-day notice is a separate document from the additional bill. It must name the specific collection actions planned and state a deadline. A generic final notice does not satisfy the requirement.
How Does the 120-Day Hold Affect DSO and Bad Debt Reserve?
The hold pushes the earliest write-off or placement decision out by roughly five months. For practices with meaningful self-pay volume, days sales outstanding rises on the patient-responsibility portion of AR.
Three modeling adjustments follow:
- Extend the self-pay aging horizon before any bad debt reserve is booked
- Separate the insurance AR curve from the patient AR curve in reporting
- Expect a larger active payment plan book, since plans are now a legal prerequisite
Practices treating patient AR and payer AR in a single aging report will misread their own collection performance under this law.
What Must Change in Collection Agency Contracts?
Vendor obligations flow through. A collection agency working New Jersey accounts must comply with the same rules, and the provider carries the risk if it does not.
| Contract Term | What It Must Cover |
|---|---|
| Compliance flow-down | Agency bound to N.J.S.A. 56:11-56 et seq. in full |
| Disclosure language | 14-point boldface statement on all communications |
| Reporting suppression | No furnishing of covered NJ medical debt |
| Debt sale prohibition | No onward sale absent a binding written agreement |
| Appeal freeze protocol | Immediate stop on notice of a pending coverage appeal |
| Indemnification | Coverage for violations and for preemption reversal |
| Audit rights | Provider access to communication samples and timing logs |
Debt sale carries its own rule. A medical creditor cannot sell patient debt unless a legally binding written agreement first prohibits the buyer from reporting the debt or pursuing judicial collection.
How Does the Act Interact With Other NJ Billing Rules?
The Act does not operate alone. Three other frameworks apply to the same self-pay balance, and their clocks run in parallel rather than in sequence.
| Framework | What It Requires | Interaction Point |
|---|---|---|
| NJ Charity Care | Eligibility screening before collections | Screening must resolve while the 120-day clock runs |
| IRS §501(r) | Reasonable efforts before extraordinary collection actions | 120-day federal notification period overlaps the state hold |
| NJ OON Act | Pre-service disclosure and arbitration on disputed balances | Arbitration is a pending dispute, freezing collection |
| NJ Prompt Pay Law | Carrier payment deadlines and appeal rights | Provider appeal makes the balance a pending review |
The sequencing trap is the appeal freeze. A provider running a prompt pay appeal on a claim cannot pursue the patient for the balance while that appeal is open. Many practices escalate to the patient precisely when the payer appeal is active.
For the full set of state rules that apply alongside this Act, see our guide to New Jersey medical billing laws. For carrier payment deadlines and interest recovery, see our breakdown of the New Jersey Prompt Pay Law.
What Are the Penalties for Non-Compliance?
Three consequences attach, and one common assumption about the fourth is wrong.
Voided debt. Any portion of a medical debt furnished to a consumer reporting agency in violation of the Act is void. The balance is not just uncollectable through that channel. It is extinguished.
New Jersey Fair Credit Reporting Act violation. Undertaking a collection action in violation of the Act is a violation of P.L.1997, c.172, which carries its own civil penalty structure.
Restitution. After a hearing and a finding of a violating practice, the Attorney General may order that any money or property acquired through the practice be restored to the affected party.
Who Enforces the Act?
The Office of the Attorney General holds sole and exclusive enforcement authority. This is stated directly in N.J.S.A. 56:11-62(d).
There is no private right of action. The statute expressly bars any private claim arising solely from a violation of the Act. Several published summaries imply patient-side civil liability. The text says otherwise.
That narrows the litigation risk considerably. It does not narrow the compliance risk, because voided debt and restitution both bite without any lawsuit being filed.
Louisa Carman Act Compliance Checklist for NJ Practices
| Requirement | Control You Need in Place |
|---|---|
| Credit reporting ban | Bureau furnishing suppressed for all covered NJ accounts |
| 120-day hold | Self-pay aging gate at day 120, tagged at registration |
| Payment plan offer | Documented offer with patient response recorded before day 120 |
| Plan terms | 3% income cap, six-month to five-year term, 60-day grace, 3% interest ceiling |
| 30-day notice | Separate notice document naming specific actions and a deadline |
| Disclosure language | 14-point boldface statement on every collection communication |
| Interest cap | 3% per annum applied to balances and judgments |
| Garnishment screening | Income verified against 600% FPL before any garnishment |
| Appeal freeze | Automatic collection stop when an internal or external review opens |
| Delete-on-notice | Process to instruct bureaus to delete on appeal or payment |
| Debt sale | Binding written agreement executed before any assignment |
| Vendor compliance | Flow-down clauses, indemnification, and audit rights in agency contracts |

How Transcure Handles NJ Medical Debt Compliance
Transcure operates as a certified New Jersey third-party billing service across the full revenue cycle. Our New Jersey workflows are configured to the Act rather than adapted to it after the fact.
That covers self-pay aging gates at day 120 and day 150, documented payment plan offers with recorded patient response, disclosure language built into statement templates, and automatic collection holds when a payer appeal opens.
For practices comparing vendors, our list of top medical billing companies in New Jersey covers what to verify before signing.
Frequently Asked Questions
What Is the Louisa Carman Medical Debt Relief Act?
It is a New Jersey law at N.J.S.A. 56:11-56 et seq. that regulates medical debt reporting and collection. Signed July 22, 2024 as P.L.2024, c.48, it bans credit reporting of covered medical debt, requires a 120-day pre-collection hold, caps interest at 3%, and mandates payment plan offers.
When Did the Louisa Carman Act Take Effect?
In two stages. The credit reporting ban and the voided-debt penalty took effect immediately on July 22, 2024. All remaining provisions, including the 120-day hold, the interest cap, and the garnishment ban, took effect on July 22, 2025. Every provision is now in force.
Can Wages Be Garnished for Medical Debt in NJ?
Only above an income threshold. The Act bars wage garnishment for any patient with annual income below 600% of the federal poverty level. Providers must verify income before pursuing garnishment. Garnishing without a documented income screen creates violation exposure under the Act.
What Is the Statute of Limitations on Medical Debt in New Jersey?
New Jersey applies a six-year limitations period to contract-based debt, including most medical debt. The Louisa Carman Act does not change that period. It changes what a creditor may do within it, by adding the 120-day hold and the pre-collection notice requirement.
What Happens if You Don’t Pay Medical Debt in NJ?
Providers may still bill, offer payment plans, and eventually pursue collection after day 150. They cannot report the debt to a credit bureau for services on or after July 22, 2024. They cannot charge more than 3% interest or garnish wages below 600% of the federal poverty level.
Is Medical Debt Still Banned From Credit Reports in New Jersey?
Yes. The New Jersey ban remains enforceable as of August 2026. A Texas federal court held in August 2026 that the Fair Credit Reporting Act preempts a similar Texas ban. That ruling does not bind New Jersey, and contrary appellate authority exists in the First, Second, and Ninth Circuits.
Does the Act Apply to Small Physician Practices?
Yes. The definition of medical creditor covers any entity owed money for health care services, with no size threshold. Solo practitioners, group practices, surgery centers, and dental offices all fall within scope. Only cosmetic procedure balances are carved out of the definition of health care service.