

California billing laws govern claims submission, payment deadlines, patient data, and debt collection statewide. Federal mandates set the floor, and California statutes often add requirements above it. Providers must follow both layers.
Several rules changed in 2025 and 2026. AB 3275 now sets a 30-calendar-day claim payment standard, and SB 1061 bans reporting medical debt to credit bureaus. This guide covers those changes, along with AB 72, HIPAA, and the CMIA.
Each of the 15 laws below lists its deadlines, penalties, and the billing steps affected. Entries on patient financial rights come first. Practices can apply them in-house or with help from a California medical billing company.
| Law | What it Requires | Effective |
|---|---|---|
| AB 72 | Limits out-of-network billing at in-network facilities to in-network cost-sharing | July 1, 2017 |
| SB 1061 | Bans reporting medical debt to credit bureaus | January 1, 2025 |
| AB 3275 and Prompt Payment | Plans and insurers pay claims within 30 calendar days | January 1, 2026 |
| Federal No Surprises Act | Covers air ambulance and requires Good Faith Estimates for self-pay patients | January 1, 2022 |
| Knox-Keene Act | Sets claims handling, emergency billing, and grievance rules for health plans | 1975 |
| Medi-Cal Billing Rules | Sets a 6-month billing limit from the month of service, plus enrollment and authorization rules | Ongoing |
| Workers’ Compensation Billing | Requires payment within 45 calendar days and IBR requests within 30 days | Ongoing |
| HIPAA | Protects patient health information, with penalties up to $73,011 per violation | Amounts effective January 28, 2026 |
| CMIA | Requires written authorization before disclosing medical information | 1981 |
| AB 716 | Caps ground ambulance patient costs at in-network cost-sharing | January 1, 2024 |
| AB 1020 and AB 2297 | Extend hospital and emergency physician financial assistance to 400% FPL and remove asset tests | 2022 and January 1, 2025 |
| Rosenthal Act | Bans abusive debt collection by creditors and collectors | 1977 |
| SB 351 | Restricts corporate influence in medicine, including billing and coding | January 1, 2026 |
| SB 306 and SB 1120 | Phase out prior authorization for high-approval services and limit medical necessity decisions to licensed clinicians | 2025 to 2026 |
| Price Transparency | Requires hospitals to publish standard charges and 300 shoppable services | January 1, 2021 |
Law 1: Assembly Bill 72 (AB 72) Balance Billing and Surprise Bill Protection Law
Assembly Bill 72 (AB 72) is California’s primary law protecting patients from surprise out-of-network bills. Patients owe only in-network cost-sharing when a noncontracting professional treats them at an in-network facility for non-emergency care.
Governor Brown signed the bill in 2016. Plans issued, amended, or renewed on or after July 1, 2017 must follow its rules.
Coverage extends to plans regulated by the Department of Managed Health Care (DMHC) or the Department of Insurance (CDI). Medi-Cal, Medicare, and self-insured plans are exempt.

What Does AB 72 Cover?
- Non-emergency Services at In-network Facilities: Noncontracting professionals cannot bill patients beyond in-network cost-sharing for covered care at a contracting facility.
- Facility Definition: AB 72’s definition of an in-network facility extends beyond the hospitals and surgery centers the federal act names.
- Ancillary Specialties: Services from anesthesiologists, radiologists, and pathologists commonly trigger the protection, because patients rarely choose these providers.
- Emergency Care: Emergency billing falls under the Knox-Keene Act, which separately protects patients from balance billing.
What Are the Key Billing Requirements Under AB 72?
The table summarizes the core duties for California providers and health plans.
| Requirement | Detail | Applies to |
|---|---|---|
| In-network cost-sharing only | Patients owe in-network rates for covered non-emergency care at in-network facilities | Noncontracting professionals |
| Default payment rate | Plans pay at least the average contracted rate and at least 125% of the Medicare rate unless the parties agree otherwise | Health plans and insurers paying noncontracting claims |
| Written consent | Written consent 24 hours in advance, with a written cost estimate | Providers billing out-of-network rates |
| Dispute process | Plan and provider resolve payment disputes through independent dispute resolution | Plans and noncontracting providers |
How Does AB 72 Work With the Federal No Surprises Act?
The federal No Surprises Act took effect on January 1, 2022. DMHC confirmed in March 2022 that AB 72 qualifies as a specified state law under the federal act. State-regulated plans therefore follow AB 72 for non-emergency out-of-network care at in-network facilities.
Self-funded employer plans and air ambulance claims instead fall under the federal act. Billing teams should identify the plan type first, since it decides which rules and dispute process apply.
Law 2: Senate Bill 1061 (SB 1061) Medical Debt Credit Reporting Ban
Senate Bill 1061 (SB 1061) bars providers, billing vendors, and debt collectors from reporting medical debt to credit bureaus. Governor Newsom signed it on September 24, 2024, and the reporting ban took effect on January 1, 2025.
Senator Monique Limón (D-Santa Barbara) authored the bill. It separates medical debt from personal credit scores, and the covered debt includes medical bills that are not past due or are already paid.
What Are the Core Rules Under SB 1061?
- Reporting Ban: Providers, billing vendors, and collection agencies cannot provide medical debt information to any credit reporting agency, regardless of the debt’s amount or age.
- Credit Decision Ban: Anyone who uses a credit report in a credit transaction cannot treat listed medical debt as a negative factor.
- Void Debt Penalty: A debt becomes void and unenforceable when a person knowingly reports it to a credit bureau.
- Narrow Exceptions: The law exempts a consumer who received direct insurer payment for the services and failed to pass it to the provider. Medical debt incurred on a credit card is also exempt.
What Contract Language Does SB 1061 Require?
Since July 1, 2025, every contract that creates medical debt must include this statutory language from Civil Code Section 1785.27. Without it, the contract is void and unenforceable.
“A holder of this medical debt contract is prohibited by Section 1785.27 of the Civil Code from furnishing any information related to this debt to a consumer credit reporting agency. In addition to any other penalties allowed by law, if a person knowingly violates that section by furnishing information regarding this debt to a consumer credit reporting agency, the debt shall be void and unenforceable.”
How Does SB 1061 Affect Billing Departments?
The table shows how SB 1061 affects billing departments and the required actions.
| Area | Required action | In Effect |
|---|---|---|
| Credit reporting workflow | Remove medical debt reporting from collection agency agreements | January 1, 2025 |
| Third-party billing vendors | Update vendor contracts to prohibit credit bureau reporting | January 1, 2025 |
| Patient financial contracts | Add the Civil Code §1785.27 language to financial agreements and payment plans | July 1, 2025 |
| Out-of-state treatment | Apply the contract language to covered California patient contracts | July 1, 2025 |
| Staff training | Train billing and collections staff on the reporting ban and contract rule | Ongoing |
Patients can sue a provider or collector that reports medical debt and file complaints with the Department of Financial Protection and Innovation or the Attorney General.
Law 3: Prompt Payment and Timely Filing Laws (AB 3275)
California sets deadlines on both sides of a claim, since providers must file on time and plans must pay on time. Assembly Bill 3275 (AB 3275) rewrote the payer side for claims received on or after January 1, 2026.
Governor Newsom signed AB 3275 on September 27, 2024. It amends Health and Safety Code §§ 1371 and 1371.35, Insurance Code § 10123.13, and Welfare and Institutions Code § 14093.08.
Filing windows vary by payer. Medi-Cal, Medicare, workers’ compensation, and commercial plans each set their own deadlines, and missing one can reduce or end payment.
What Did AB 3275 Change About Payer Deadlines?
Before 2026, plans had 30 working days to reimburse, contest, or deny a complete claim, and HMOs had 45. AB 3275 replaced both with a standard 30-calendar-day timeline for HMOs, Medi-Cal managed care plans, and health insurers.
The new count includes weekends and holidays, and it applies to claims received on or after January 1, 2026. Claims received earlier stay under the working-day timelines.
Interest and penalties apply to any claim unpaid after 30 calendar days, including emergency claims, and plans must add accrued interest without waiting for a request. Repeated failures can count as an unfair payment pattern.
The plan must issue a written determination within 45 working days after receiving a provider dispute.
What Are the Payment and Filing Deadlines by Payer Type?
Payer deadlines appear in the first table.
| Payer type | Payment deadline | Notes |
|---|---|---|
| Commercial plans, HMOs, and health insurers | 30 calendar days | Applies to claims received on or after January 1, 2026 |
| Medi-Cal managed care plans | 30 calendar days | Included under AB 3275 |
| Workers’ compensation carriers | 45 calendar days | Late payment adds a 15% penalty plus interest under Labor Code §4603.2 |
Provider filing windows follow in the second table.
| Payer type | Filing window | Basis |
|---|---|---|
| Commercial plans | Set by the provider contract | Check each contract |
| Medi-Cal | 6 months from the month of service | Welfare and Institutions Code §14115 |
| Medicare | 12 months from the date of service | 42 CFR §424.44 |
| Workers’ compensation | 12 months from the date of service or discharge | Labor Code §4603.2, with a 30-day window for some bills |
What Happens When a Provider Misses a Filing Deadline?
Consequences depend on the payer. Medi-Cal reduces payment for claims 6 to 12 months late, and many plans deny claims past 1 year unless an exception applies. Commercial plans follow their contracts and may deny late claims under those terms.
How Should Billing Teams Adjust to AB 3275?
Billing teams should reset follow-up calendars to count payer deadlines in calendar days for claims received on or after January 1, 2026. Flag unpaid claims at day 30 for status checks or provider disputes, and confirm that every late payment includes interest.
For Medi-Cal, log each service month and keep delay documents for every exception claim. Review each commercial contract for its filing window.
Law 4: Federal No Surprises Act (NSA)
The No Surprises Act (NSA) took effect on January 1, 2022. It bans balance billing for emergency care and certain out-of-network care at in-network facilities and adds air ambulance protections. It also requires Good Faith Estimates for uninsured and self-pay patients.
In California, state-regulated plans follow AB 72 and the Knox-Keene Act for most of these situations. The federal act mainly reaches self-funded employer plans and air ambulance claims.
What Does the No Surprises Act Cover?
The act requires emergency services to be billed at in-network cost-sharing, no matter the hospital’s or provider’s network status. It also limits out-of-network billing for non-emergency care at in-network facilities and protects patients from out-of-network air ambulance bills.
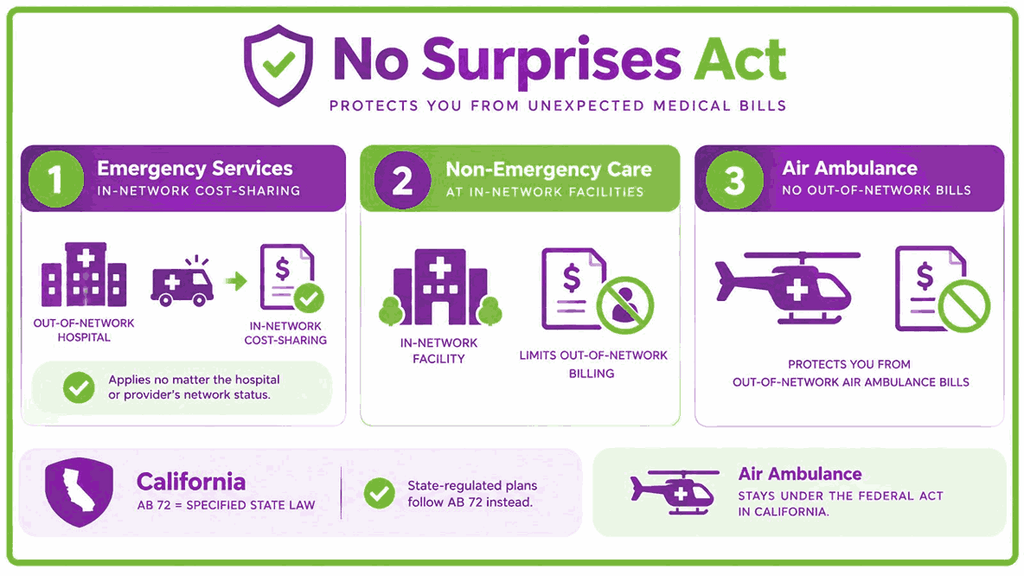
DMHC confirmed in March 2022 that AB 72 qualifies as a specified state law, so state-regulated plans follow it instead. Air ambulance claims stay under the federal act in California.
When Can an Out-of-Network Provider Use Notice and Consent?
A non-emergency provider can ask a patient to waive balance billing protections, but only with written notice and consent. The notice must reach the patient at least 72 hours before a scheduled service. For a service booked within 72 hours, send notice on the day of scheduling and at least 3 hours before care.
Providers should use the CMS standard form and include a Good Faith Estimate of charges.
Ancillary services cannot use this exception. Anesthesia, radiology, pathology, and similar services remain protected because patients rarely choose those providers. Consent also doesn’t apply when no in-network alternative exists.
What Are the Good Faith Estimate Rules?
Providers must give uninsured and self-pay patients a written estimate of expected charges before scheduled care. A patient whose final bill exceeds the estimate by $400 or more can start a dispute process with HHS. The patient has 120 days from the bill date to file.
Patients enrolled in Medicare or Medicaid are not entitled to a Good Faith Estimate under the federal process.
Which Law Governs Each Plan Type?
Billing teams should identify the plan type first, since it decides which rules and dispute process apply.
| Plan Type | Governing Law | Dispute Process |
|---|---|---|
| Fully insured, state-regulated plans | AB 72 for non-emergency care at in-network facilities, Knox-Keene for emergency care | California independent dispute resolution |
| Self-funded employer (ERISA) plans | Federal No Surprises Act | Federal independent dispute resolution |
| Air ambulance claims | Federal No Surprises Act | Federal independent dispute resolution |
| Medicare Advantage plans | Federal Medicare rules | Medicare appeals process |
| Medi-Cal managed care plans | DHCS rules and Knox-Keene | DHCS grievance process |
Law 5: Knox-Keene Health Care Service Plan Act
The Knox-Keene Health Care Service Plan Act of 1975 is California’s foundational law for HMOs and managed care plans. The Department of Managed Health Care (DMHC) administers it and sets standards for how plans contract with providers, process claims, and handle disputes.
The Act shapes billing in two ways. DMHC enforces its claims-payment rules, and plan contracts with providers must follow them. It also works alongside AB 72 to protect patients from out-of-network bills.
Which Claims Processing Rules Apply to Plans?
Plans must reimburse a complete claim within 30 calendar days of receipt, and they must tell the provider in writing within the same 30 days if they contest or deny a claim. Interest accrues at 15% per year starting the first calendar day after day 30.
Before 2026, the deadline was 30 working days, or 45 for HMOs. A provider who disputes a decision should expect a written determination within 45 working days.
| Rule | Requirement |
|---|---|
| Claim payment | 30 calendar days from receipt of a complete claim |
| Contested or denied claim notice | Written notice within 30 calendar days |
| Late payment interest | 15% per year after the 30 days |
| Provider dispute determination | Written determination within 45 working days |
| Standard patient grievance | Resolved within 30 calendar days |
| Urgent patient grievance | Resolved within 72 hours |
Law 6: Medi-Cal Billing Regulations
Medi-Cal is California’s Medicaid program, funded by the state and federal governments. The Department of Health Care Services (DHCS) administers it, and the Centers for Medicare and Medicaid Services (CMS) provides federal oversight.
Providers who bill Medi-Cal must follow enrollment, authorization, and coding rules that differ from those for commercial and Medicare billing. Errors in any of them lead to denials or reduced payment.
What Are the Core Medi-Cal Billing Requirements?
Under Medi-Cal billing regulations, providers must have active Medi-Cal enrollment before billing and revalidate it through the PAVE system every 5 years. Claims under an inactive or incorrect enrollment are denied.
Many services require prior authorization before care, so staff should first check coverage in the Medi-Cal Provider Manual, since commercial coverage rules do not carry over.
Claims follow a 6-month billing limit measured from the month of service. Late claims need a delay reason code and supporting documents, and claims sent between 6 and 12 months out without an exception face a payment reduction.
How Do Medi-Cal Rates Work After the 2024 Increase?
On January 1, 2024, DHCS raised rates for targeted services to at least 87.5% of the Medicare rate for the lowest-paying locality in California. The increase covers primary care, maternity care, and non-specialty mental health services.
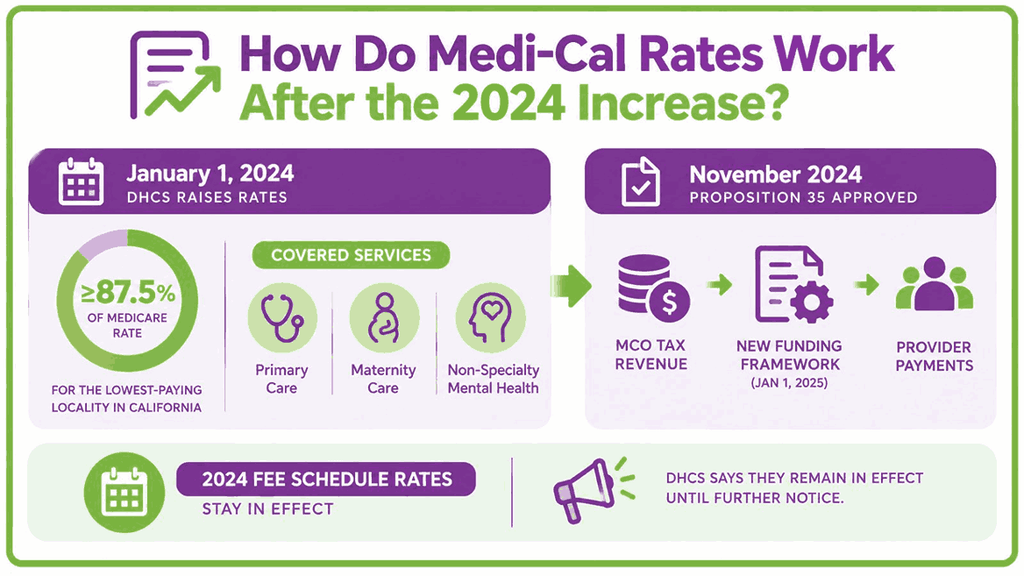
Proposition 35, approved in November 2024, now sets the framework for how MCO tax revenue funds provider payments from January 1, 2025. DHCS says the 2024 fee schedule rates stay in effect until further notice.
What Causes the Most Medi-Cal Claim Errors?
The table below shows the compliance areas and requirements that cause most Medi-Cal claim errors.
| Compliance Area | Requirement | Common Error |
|---|---|---|
| Provider enrollment | Active enrollment before submission | Billing under an expired NPI or inactive enrollment |
| Service authorization | Authorization documented before billing | Using the wrong authorization number |
| Coding accuracy | ICD-10-CM and CPT codes match documented services | Upcoding or using non-covered procedure codes |
| Timely submission | 6 months from the month of service | Missing the window without a delay reason |
| Retroactive eligibility | Bill covered services within the retroactive period using delay reason code 8 | Writing off the claim before checking eligibility |
Law 7: California Workers’ Compensation Billing Laws (Labor Code §4603.2)
Workers’ compensation billing in California follows its own framework under the Labor Code and the Division of Workers’ Compensation (DWC). Labor Code §4603.2 sets the payment timelines, and the Official Medical Fee Schedule (OMFS) sets reimbursement rates for services to injured workers.
These claims follow a different path than commercial claims. Providers submit bills in the workers’ compensation format, and payers review them before any dispute escalates.
How Does the Dispute Process Work?
A provider who disputes the amount paid has 90 days from service of the explanation of review to request a second review. Missing that window leaves the bill deemed satisfied, and neither the employer nor the worker owes more.
If the second review does not settle the dispute, the provider has 30 days from service of that second review to request independent bill review (IBR). A missed IBR window also leaves the bill deemed satisfied.
What Deadlines Should Billing Teams Track?
Here are the deadlines every billing team should know when working with workers’ compensation billing, along with the consequences.
| Step | Deadline | Consequences |
|---|---|---|
| Submit the bill | 12 months from the date of service or discharge | Payment and lien rights at risk |
| Carrier pays with an explanation of review | 45 calendar days | 15% penalty plus interest |
| Request second review | 90 days from service of the explanation of review | Bill deemed satisfied |
| Request independent bill review | 30 days from service of the second review | Bill deemed satisfied |
| File a lien (Labor Code §4903.5) | 12 months from knowing an injury is claimed, and within 5 years of service | Worker owes nothing on the obligation |
Payment follows the fee schedule in effect on the date of service. DWC sets a 30-day submission window for some bills, such as services exempt from prospective review.
Law 8: Health Insurance Portability and Accountability Act (HIPAA)
HIPAA, enacted in 1996 and administered by the U.S. Department of Health and Human Services (HHS), sets the federal baseline for protecting patient health information in billing and clinical operations. It applies to covered entities in California, including physician practices, health plans, and clearinghouses, as well as their business associates.
The Privacy Rule governs how covered entities use and disclose protected health information (PHI). The Security Rule sets safeguards for electronic PHI, and the Breach Notification Rule sets reporting duties after a breach.
For penalties assessed on or after January 28, 2026, civil fines run from $145 to $73,011 per violation across four culpability tiers, with an annual cap of $2,190,294 per identical provision. OCR applies reduced annual caps for Tiers 1 through 3 under its enforcement discretion.
What Billing Requirements Does HIPAA Set?
Billing staff may access only the PHI needed for their function, since claims submission does not require a full medical record. Any billing company, clearinghouse, or collection agency that handles PHI must sign a Business Associate Agreement (BAA) before receiving patient data.
Electronic claims must use standard HIPAA formats: 837P for professional claims, 837I for institutional claims, and 835 for remittance advice.
Practices that bill federal programs often follow OIG’s seven-element compliance guidance. It covers written policies, a compliance officer, staff training, reporting channels, discipline, auditing, and prompt response to violations.
What Are the HIPAA Breach Notification Deadlines?
Deadlines depend on who must be notified and how many people the breach affects.
| Who is notified | When it applies | Deadline |
|---|---|---|
| Affected individuals | Any breach of unsecured PHI | Without unreasonable delay, within 60 calendar days of discovery |
| HHS | 500 or more individuals affected | Within 60 calendar days of discovery |
| HHS | Fewer than 500 individuals affected | Within 60 days after the end of the calendar year |
| Prominent media | More than 500 residents of one state | Within 60 days of discovery |
| Covered entity | Breach at a business associate | Within 60 calendar days of discovery |
Law 9: California Confidentiality of Medical Information Act (CMIA)
The California Confidentiality of Medical Information Act (CMIA), found at Civil Code §56 et seq., is California’s main medical privacy statute. Enacted in 1981, it predates HIPAA by 15 years.
It bars providers, health plans, and contractors from disclosing medical information without the patient’s or their representative’s valid written authorization.
CMIA applies to billing because claims processing involves accessing, transmitting, and disclosing identifiable medical information. A billing department that shares data with insurers, clearinghouses, or collection agencies must follow its disclosure rules.
What Does CMIA Require From Billing Departments?
Disclosures outside treatment and payment require written authorization in at least 14-point type, kept clearly separate from other document text. Store and dispose of records and billing documents in ways that protect confidentiality.
Electronic billing systems must log access and record changes or deletions, including who made them and when. Third-party billing companies that handle CMIA-protected data must agree to the same confidentiality requirements as the provider.
What Are the CMIA Penalties?
A patient can sue for $1,000 in nominal damages per violation without proving actual harm, plus actual damages when they exist. Civil penalties reach $2,500 per negligent violation and $25,000 per knowing and willful violation.
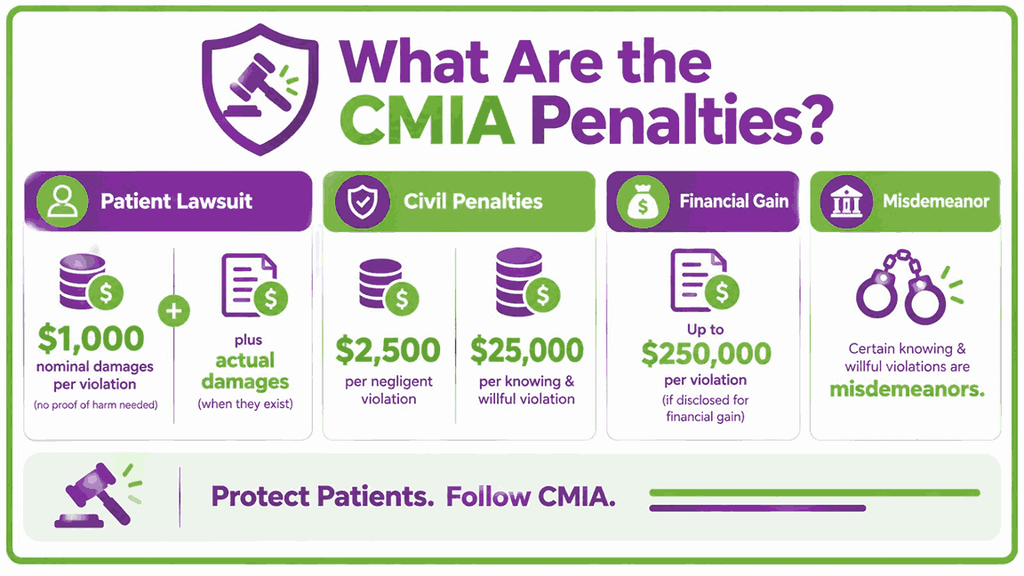
A disclosure made for financial gain can carry a penalty of up to $250,000 per violation. Certain knowing and willful violations are also misdemeanors.
How Do CMIA and HIPAA Differ?
The table below shows the differences between CMIA and HIPAA and which areas come under them.
| Area | HIPAA | CMIA and California law |
|---|---|---|
| Private right of action | None | Patients can sue, with $1,000 nominal damages per violation |
| Civil penalties | Tiered fines up to $73,011 per violation, with a $2,190,294 annual cap | Up to $2,500 negligent, $25,000 knowing and willful, and $250,000 for financial gain |
| Patient record access | 30 days, with one extension | 5 working days to inspect and 15 days for copies under Health and Safety Code §123110 |
| Breach reporting for licensed clinics and facilities | 60 days to notify individuals | 15 business days to report to the state and notify patients under Health and Safety Code §1280.15 |
California providers must meet both sets of rules. In billing, the CMIA often drives disclosure decisions because of its private right of action and its access deadlines.
Law 10: Assembly Bill 716 (AB 716) Ground Ambulance Balance Billing Law
Assembly Bill 716 (AB 716) extends balance billing protection to ground ambulance services in California. Governor Newsom signed it on October 3, 2023, and it took effect on January 1, 2024.
Before AB 716, neither AB 72 nor the federal No Surprises Act covered ground ambulance service bills. The law applies to state-regulated plans and insurers, so self-funded employer plans fall outside it. Medi-Cal beneficiaries stay under their existing protections.
What Does AB 716 Require for Insured Patients?
An insured patient owes only the in-network cost-sharing amount for a noncontracting ground ambulance, and that amount counts toward the deductible and out-of-pocket limit. When it pays, the insurer tells both the patient and the provider what cost-sharing is owed.
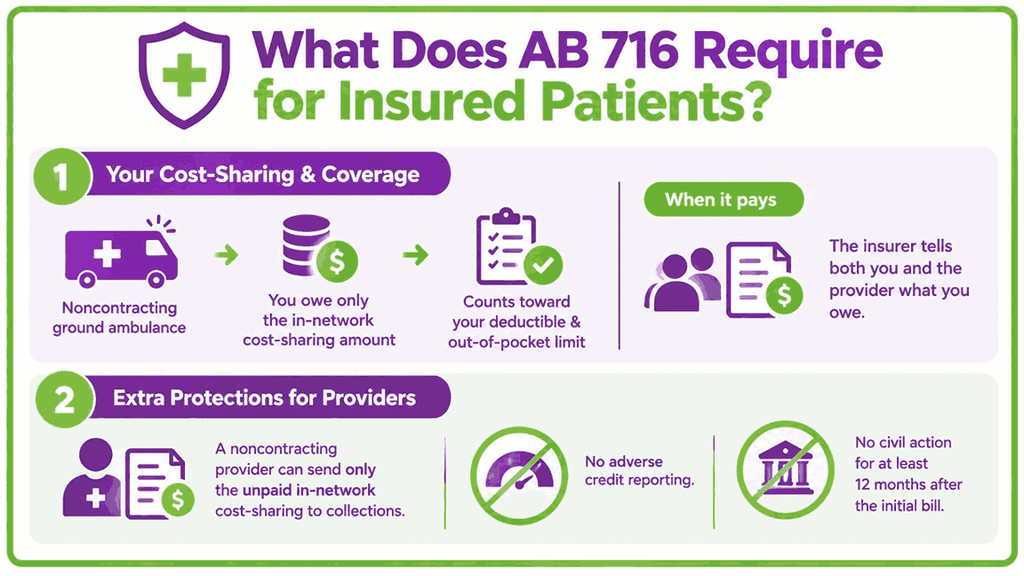
A noncontracting provider can send only the unpaid in-network cost-sharing to collections. The provider cannot report adverse information to a credit bureau or file a civil action for at least 12 months after the initial bill.
What Applies to Uninsured and Self-Pay Patients?
A ground ambulance provider cannot require an uninsured or self-pay patient to pay more than the established Medi-Cal or Medicare fee-for-service payment, which is currently the Medicare amount. Only that capped amount can go to collections.
Providers and their assignees also cannot use wage garnishment or liens on a primary residence to collect these bills.
How Must Plans Pay Noncontracting Ambulance Providers?
Plans and insurers pay the difference between the in-network cost-sharing amount and the local rate.
If a local government has set or approved a rate for the area, that rate applies; if not, the plan uses the reasonable and customary value of the service. DMHC expects plans to pay the provider directly rather than reimbursing the enrollee.
Law 11: Hospital and Emergency Physician Fair Pricing Laws (AB 1020, AB 2297, and AB 1312)
California’s Hospital Fair Pricing Act requires hospitals to keep written charity care and discount payment policies, and emergency physicians must have their own discount policies. Three laws have reshaped those rules since 2022.
AB 1020 widened eligibility, AB 2297 tightened collection practices, and AB 1312 adds presumptive screening in 2027.
The Department of Health Care Access and Information (HCAI) enforces the rules through its Hospital Fair Billing Program. The laws matter most to hospitals, emergency physician groups, and the billing teams that manage patient accounts.
What Did AB 1020 Change?
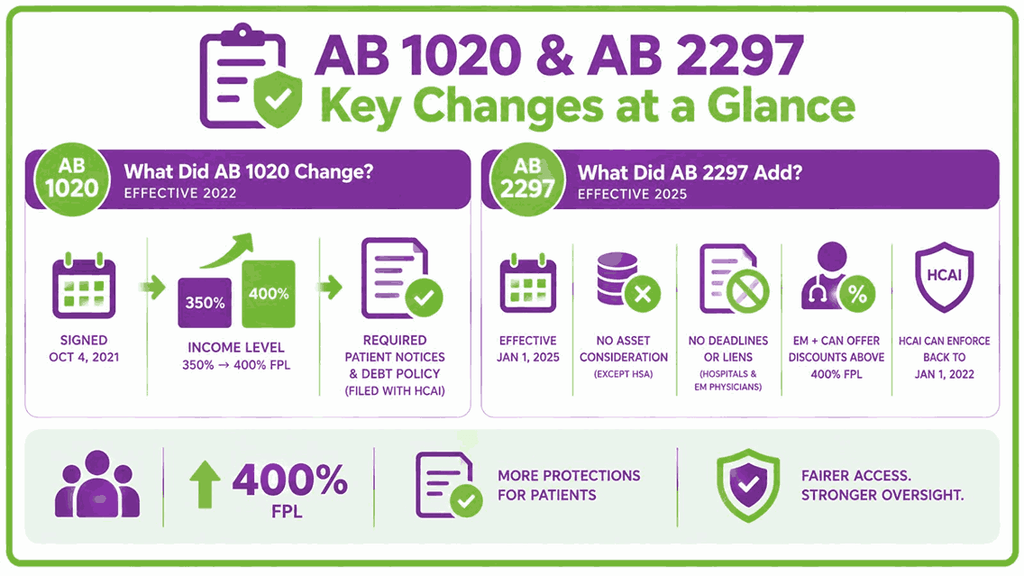
Governor Newsom signed AB 1020 on October 4, 2021, and it took effect in 2022. It raised the financial assistance income level from 350% to 400% of the federal poverty level. The law also required patient notices and a debt collection policy filed with HCAI.
What Did AB 2297 Add?
AB 2297 took effect on January 1, 2025. Hospitals cannot consider a patient’s assets, except a health savings account. Neither hospitals nor emergency physicians can set application deadlines or place liens on real property.
Emergency physicians may extend discounts above 400% of the federal poverty level, and HCAI can now enforce these rules back to January 1, 2022.
What Does AB 1312 Require Starting July 1, 2027?
Under AB 1312, the Patient Debt Prevention Act, hospitals must screen patients for presumptive eligibility for charity care and discount payment. Patients enrolled in CalFresh or CalWORKs qualify.
Hospitals must inform patients about the screening and allow them to opt out. Teams should update eligibility workflows and billing statements before the start date.
What Are the Key Dates and Requirements?
Keep these key dates and requirements in mind while working around AB 1020, AB 2297, and AB 1312.
| Law | Key Requirement | Effective |
|---|---|---|
| AB 1020 | 400% FPL eligibility, notice rules, and a 180-day pause on credit reporting and civil action | 2022 |
| AB 2297 | No asset tests, no application deadlines, no real property liens, and coverage of emergency physicians | January 1, 2025 |
| AB 1312 | Presumptive eligibility screening for charity care and discount payment | July 1, 2027 |
Law 12: Rosenthal Fair Debt Collection Practices Act (Civil Code §1788)
California’s Rosenthal Fair Debt Collection Practices Act, found at Civil Code §§1788 to 1788.33, governs how debts are collected from California consumers. It dates to 1977 and covers medical bills, so it applies to patient balances.
Unlike the federal Fair Debt Collection Practices Act (FDCPA), the Rosenthal Act reaches creditors collecting their own debts as well as third-party collectors. A practice that bills its own patients can fall under it, not just a collection agency.
What Conduct Does the Rosenthal Act Prohibit?
The Act bars harassment, false or misleading statements about a debt, and unfair collection practices. It also incorporates most of the federal FDCPA by reference, so any FDCPA violation also counts as a Rosenthal violation.
Collectors who contact patients must follow the same standards as federal law, including validation notices and honest descriptions of the amount owed.
What Are the Penalties and Time Limits for Patients to Sue?
A patient can recover actual damages, plus statutory damages of $100 to $1,000 for a willful and knowing violation, plus attorney fees. A patient has 1 year from the date of the violation to file suit.
In some cases, the Act also gives a collector 15 days after notice to cure a violation, so documenting corrections quickly can limit exposure.
Do Practices Using Billing Companies Fall Under the Act?
One 2022 appellate decision held that a medical provider using an unaffiliated third-party billing service was not itself a debt collector. The Act applies to those who regularly collect debts, so billing and collection vendors that handle patient balances can still fall within it.
Practices should confirm in vendor contracts who contacts patients, which scripts they use, and how they handle violations.
How Long Do Providers Have to Collect a Patient Balance?
Collection lawsuits face their own deadlines, and the clock depends on the type of agreement. This limit is separate from credit reporting, since SB 1061 now bars reporting medical debt to credit bureaus.
| Claim Type | Time limit | Authority |
|---|---|---|
| Written contract, such as a signed financial responsibility form | 4 years | Code of Civil Procedure §337 |
| Oral agreement | 2 years | Code of Civil Procedure §339 |
| Patient suit against a collector under the Rosenthal Act | 1 year from the violation | Civil Code §1788.30 |
Review and escalate accounts nearing the limit before it expires, since a lapsed window can end the option to bring court action.
Law 13: Senate Bill 351 (SB 351) Private Equity and Corporate Practice Restrictions
SB 351 limits how private equity groups and hedge funds can influence physician and dental practices in California. Governor Newsom signed it on October 6, 2025, and it took effect on January 1, 2026. It codifies and expands the state’s rules governing corporate practice of medicine and dentistry.
The law matters to billing because it bars these investors from controlling coding and billing decisions for patient services. Practices with outside investors, and the management companies that serve them, need clear lines on who decides what.
What Does SB 351 Prohibit?
Private equity groups and hedge funds involved in a physician or dental practice cannot interfere with professional judgment. The table lists the specific practice functions the law places off-limits.
| Area | What a private equity group or hedge fund cannot do |
|---|---|
| Coding and billing | Make decisions about coding and billing for patient services |
| Payer contracting | Set parameters for third-party payer contracts |
| Staffing | Select, hire, or fire clinicians based on clinical proficiency |
| Equipment | Approve the selection of medical equipment and supplies |
| Patient records | Own or determine the content of medical records |
| Contract terms | Impose noncompete or nondisparagement clauses, with limited exceptions |
Who Does SB 351 Apply To?
The prohibitions apply to private equity groups and hedge funds, and to entities they control, such as management service organizations. They apply no matter how the practice is structured.
Existing agreements are not grandfathered. Contract terms that violate SB 351 became void and unenforceable on January 1, 2026, even if the parties signed them earlier.
How Is SB 351 Enforced?
The California Attorney General can seek injunctive relief and recover attorneys’ fees for violations. Practices had to review their structures and contracts before the effective date, and those that haven’t done so face active exposure.
A companion law, AB 1415, also took effect on January 1, 2026. It expands the transactions that private equity groups, hedge funds, and management service organizations must report to the Office of Health Care Affordability.
What Should Practices and Billing Teams Review?
Practices with outside investors should map who makes each coding and billing decision and confirm in writing that physicians or the practice keep that authority. Start with management agreements, billing delegation clauses, and coding policies.
Billing partners should also confirm ownership and contract terms so no one outside the practice can improperly direct coding decisions.
Law 14: Prior Authorization and Utilization Review Laws (SB 306 and SB 1120)
Two California laws now shape how health plans handle prior authorization. SB 1120, known as the Physicians Make Decisions Act, limits the use of artificial intelligence in coverage decisions. SB 306 phases out prior authorization for services that plans approve at very high rates.
Both laws affect billing teams, since prior authorization sits at the front of the revenue cycle. Delays and denials at this stage carry through to the claim.
What Does SB 1120 Require?
SB 1120 took effect on January 1, 2025. It applies to health care service plans, disability insurers, and vendors that perform utilization review for them. An AI tool or algorithm cannot deny, delay, or modify care based in whole or in part on medical necessity.
A licensed physician or qualified health care provider must make those decisions. Plans must file written policies with regulators, tell members on their websites when they use AI in utilization review, and allow DMHC and CDI to audit the tools.
What Does SB 306 Require?
SB 306, the Defending Physicians Decisions Act, was signed in October 2025 and took effect on January 1, 2026. It builds a data-driven path to remove prior authorization for services that plans nearly always approve.
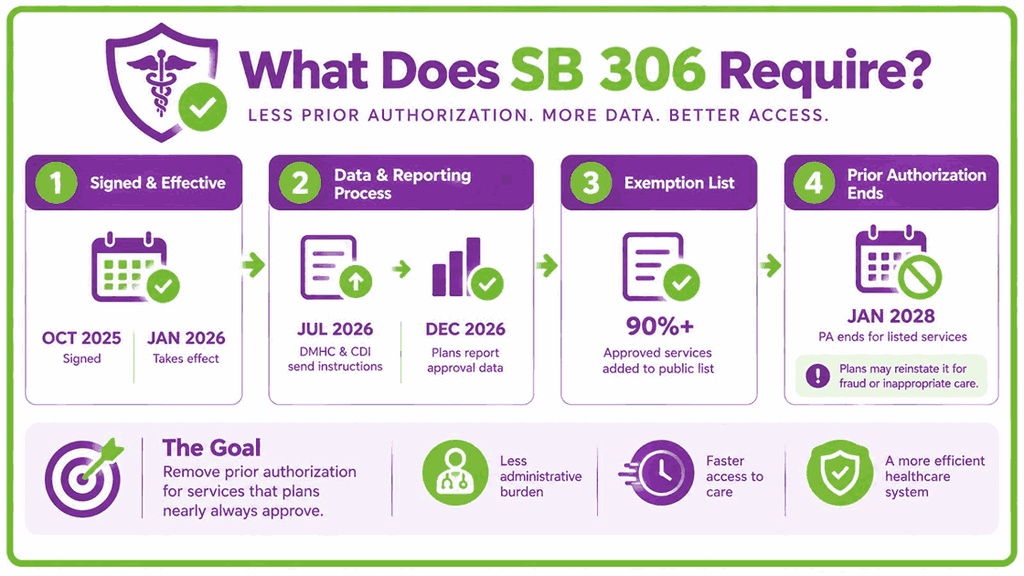
DMHC and CDI issue reporting instructions to plans by July 1, 2026. Plans then report approval data by December 31, 2026, and services approved at least 90% of the time go on a published exemption list.
Prior authorization on those services ends on January 1, 2028, though plans may reinstate it for specific providers involved in fraud or clinically inappropriate care.
How Should Billing Teams Prepare?
Track approval and denial rates by payer and service now, since the same data will drive the exemption list. When a denial arrives without physician review, ask the plan whether an automated tool made the decision.
Watch the published list in mid-2027 and update front-desk workflows before the January 2028 cutoff. A separate bill, AB 512, would have shortened plan response times, but the governor vetoed it.
Law 15: Hospital Price Transparency Laws (Federal Rule and California Requirements)
Hospital price transparency rules let patients see costs before care. The federal rule sets the main requirements, and California adds its own reporting and estimate rules on top.
Hospitals carry most of these duties. Physician offices and other non-hospital providers instead follow the No Surprises Act’s Good Faith Estimate rules, as covered in Law 4.
What Does the Federal Price Transparency Rule Require?
Under the CMS rule, which began on January 1, 2021, hospitals must post two things online.
First, they must post a machine-readable file of standard charges for all items and services. Second, they must post a consumer-friendly display of at least 300 shoppable services, including 70 CMS-specified services.
CMS finalized new machine-readable file data requirements in 2026, and enforcement began April 1, 2026.
What Does California Add?
California hospitals submit chargemaster data to HCAI, which publishes it through a public cost transparency portal. Hospitals must also provide uninsured patients with written estimates upon request.
Income-based billing limits now follow AB 1020, which sets eligibility at 400% of the federal poverty level, as covered in Law 11. Patients can also request an itemized statement from a provider.
Are There Any Upcoming California Billing Laws in 2027?
Several California laws already signed reach new milestones between December 2026 and January 2028. Prior authorization rules shift the most, and hospital charity care screening begins in July 2027.
Billing teams that plan avoid scrambling when each date arrives. The table lists every dated change and who it affects.
| Date | Law | What Changes | Who is Affected |
|---|---|---|---|
| December 31, 2026 | SB 306 | Plans and insurers report prior authorization approval data to state regulators | Health plans, insurers, and the practices they authorize |
| July 1, 2027 | AB 1312 | Hospitals begin presumptive eligibility screening for charity care and discount payment | Hospitals and their billing teams |
| July 1, 2027 | SB 306 | List of services approved at least 90% of the time is published | Practices that request prior authorization |
| January 1, 2028 | SB 306 | Plans stop requiring prior authorization for listed services | Practices that request prior authorization |
What Changes Before the End of 2026?
SB 306 sets the first deadline. Health plans and insurers must report prior authorization approval data to state regulators by December 31, 2026. The data follows instructions that DMHC and CDI were required to issue by July 1, 2026.
Billing teams do not file this report, but their payers do. The same numbers determine which services later lose prior authorization.
What Takes Effect in 2027?
Two milestones land on July 1, 2027. AB 1312 requires hospitals to screen patients for presumptive eligibility for charity care and discount payment, and patients enrolled in programs such as CalFresh or CalWORKs qualify.
Hospitals must tell patients about the screening and let them opt out. Regulators publish the list of services approved at least 90% of the time the same day. That list shows which prior authorization requirements will end.






